



Limited-Time Offer
Claim $200 OFF Any In-Person Course
Hands-on, CME-accredited training with live patients. Tell us where to send your discount.


Academy of Functional Medicine
Academy of Pain Management
Academy of Business & Marketing


Botox, Dermal Fillers, and More
IV Nutrition, Hormone Pellet, and More
Pain Show, NCV/EMG, and More
Blueprint, Business Bootcamp, and More
Facial Aesthetics, Cosmetic Laser, and More
Learn From the Comfort of Your Home or Office
A Global Community of Aesthetic Professionals
Follow a Proven Training Progression
All-Inclusive CME Plans

Discover Our 28+ Year Legacy
We're Here to Help With What You Need!
Explore World-Renowned Educators
See What Our Students Are Saying
Grow With Us
Your Production Solution
Get FREE Playbooks and Guides
Explore Valuable Information
A Customizable Training Experience
Get Up to 50% OFF Sitewide—Labor Day SaleGet Up to 50% OFF Sitewide
OFFER ENDS Fri, Sep 1800
Days00
Hrs00
Mins00
SecsBotox, Dermal Fillers, and More
IV Nutrition, Hormone Pellet, and More
Pain Show, NCV/EMG, and More
Business & Marketing Masterclass, Business Bootcamp, and More
Facial Aesthetics, Cosmetic Laser, and More
Learn From the Comfort of Your Home or Office
A Global Community of Aesthetic Professionals
Follow a Proven Training Progression
All-Inclusive CME Plans
Discover Our 28+ Year Legacy
Explore World-Renowned Educators
See What Our Students Are Saying
Explore Valuable Information
Grow With Us
Your Production Solution
Get FREE Playbooks and Guides
A Customizable Training Experience
 Sign In
Empire Medical Training's clinical knowledge base for aesthetic injectors. 104 guides across ten subjects — facial anatomy, complication recognition and response, dosing reasoning, treatment planning and patient comfort — written from what our faculty actually teach.
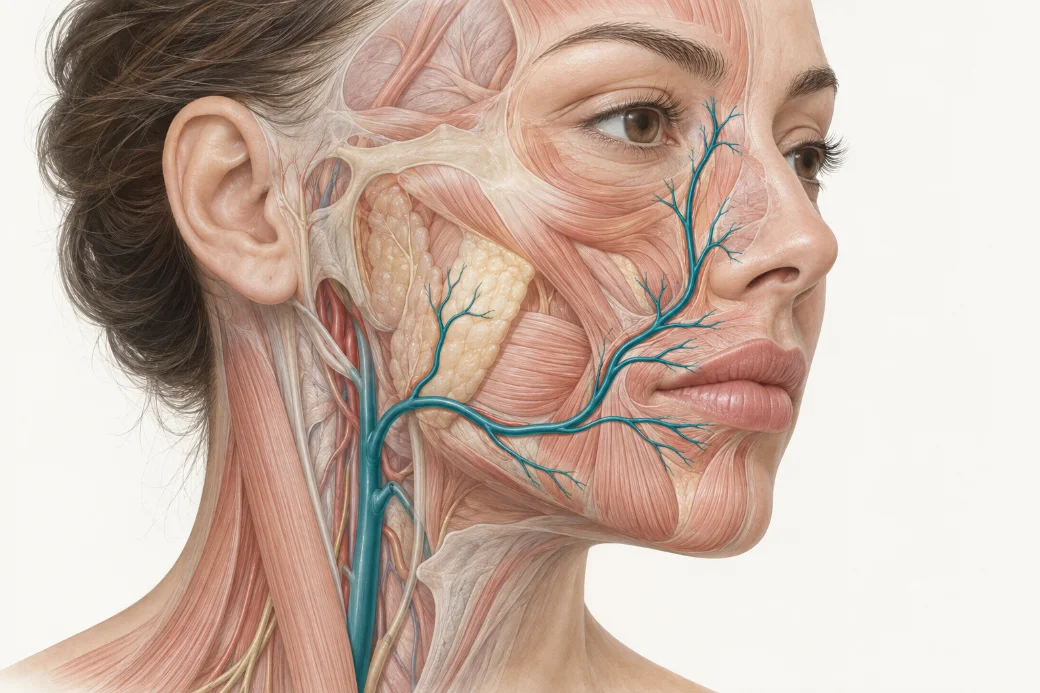
No guides match your search. Try a broader keyword.
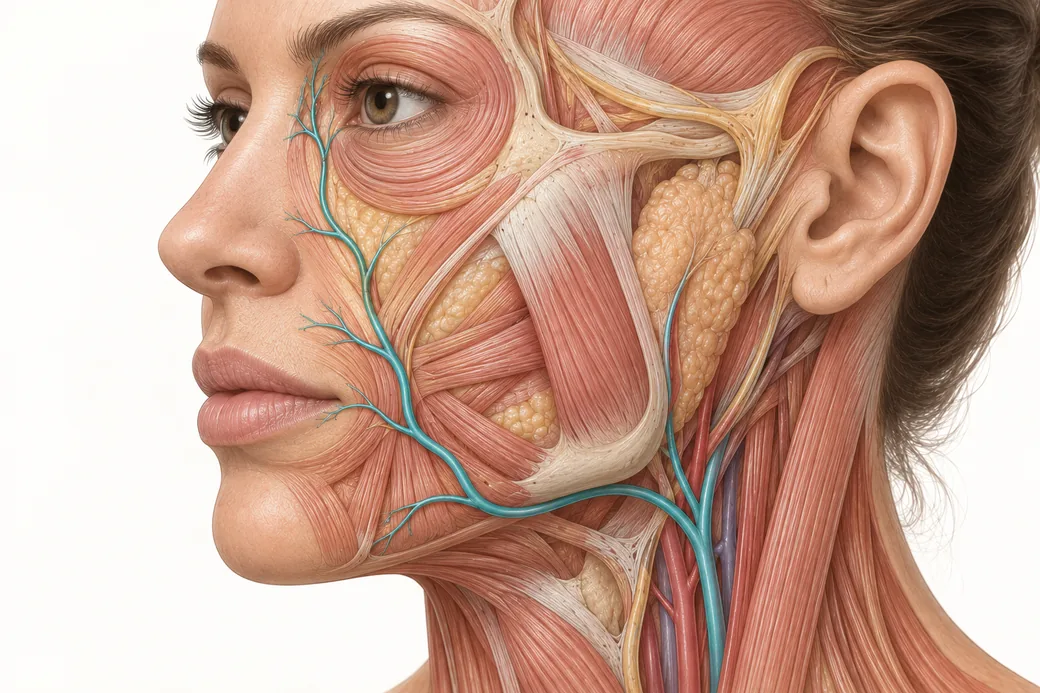 Anastomoses: Why the Complication Doesn't Appear Where You InjectedFacial artery anastomoses explain why a lip treatment causes nasal skin changes. How arterial connections
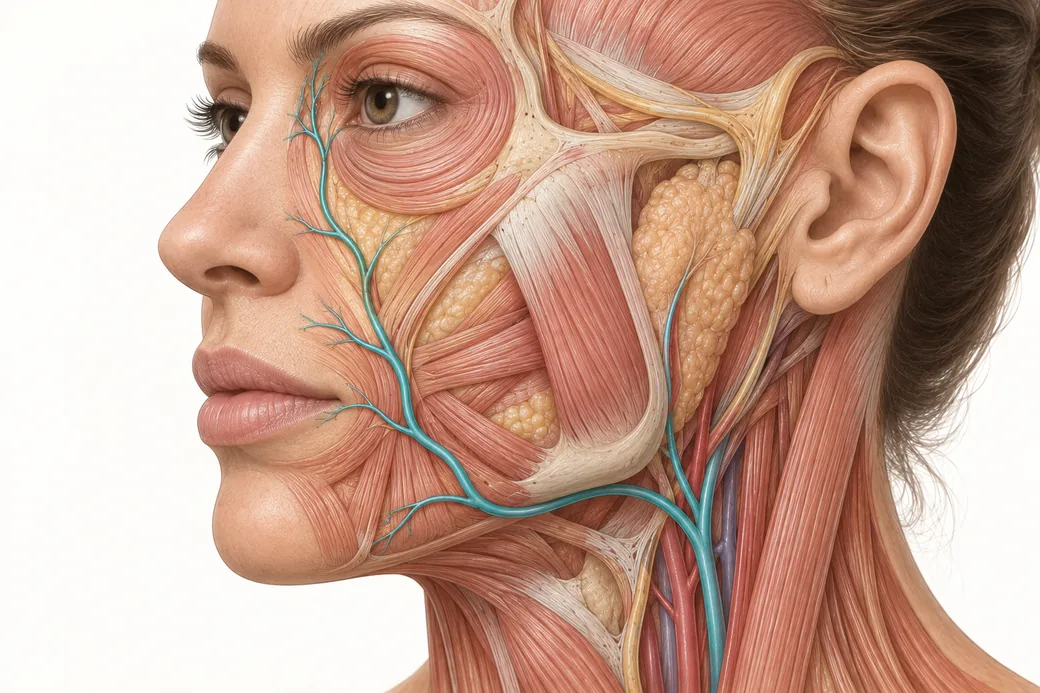 Facial Artery Variability: Why Landmarks Are Probabilities, Not CertaintiesFacial artery variability in cadaver data — termination points, branch prevalence, tortuosity and depth,
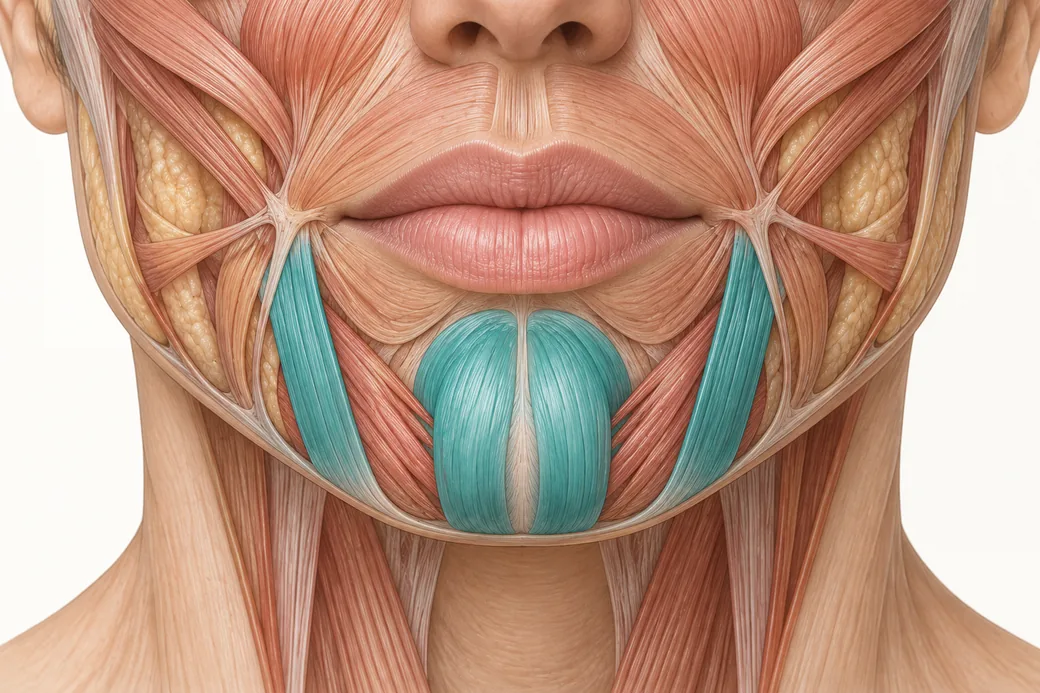 The Perioral–Nasal Corridor: Labial, Columellar and Alar Arterial AnatomyLabial artery anatomy for injectors — superior and inferior labial arteries, the columellar branch and th
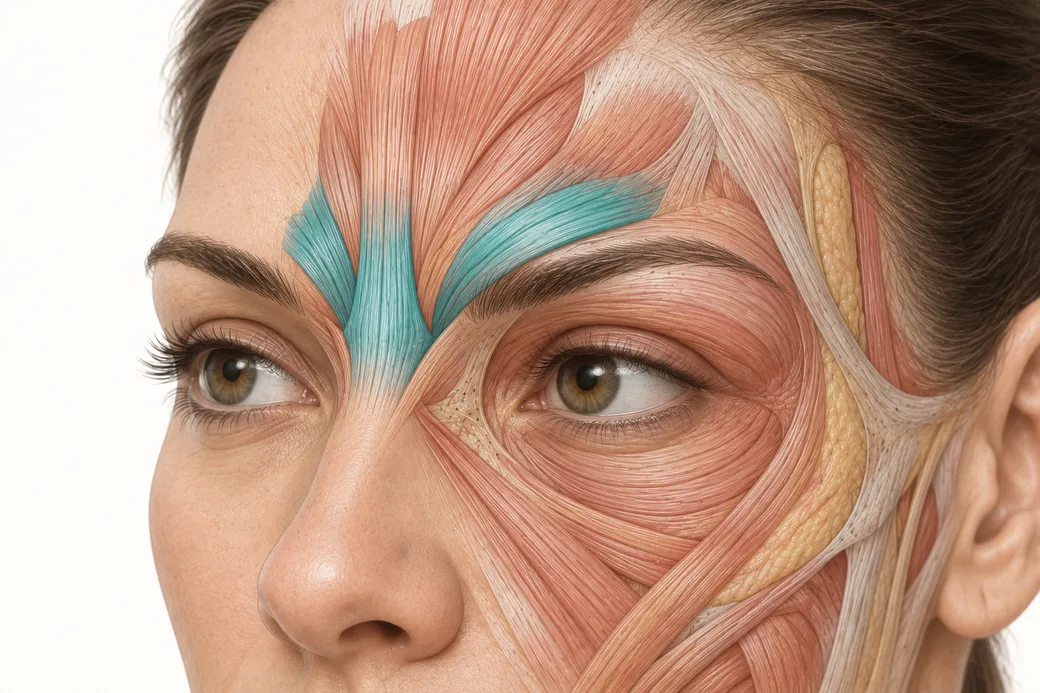 Glabella Filler Risk: The Anatomy That Makes This the Least Forgiving TerritoryWhy glabella filler risk is the highest on the face: supratrochlear and supraorbital anatomy, internal ca
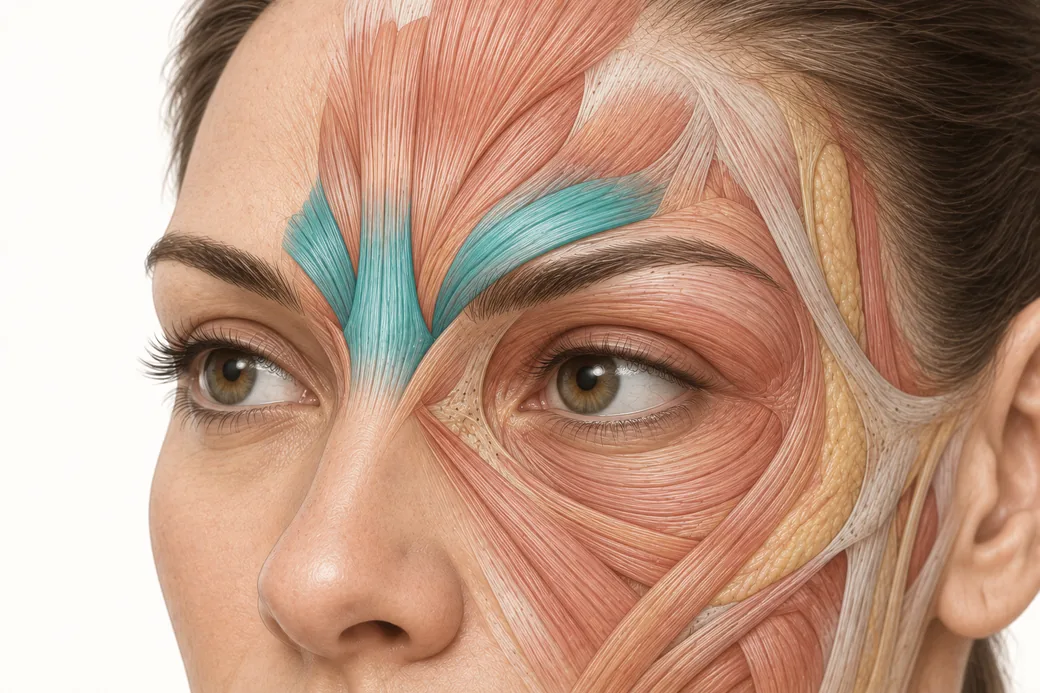 Filler Vascular Occlusion and Vision Loss: The Glabellar Crossroad, Step by StepHow filler vascular occlusion at the glabella causes vision loss — the retrograde embolic chain from the
 Needle vs Cannula Filler Decisions in High-Risk Regions: Neither Is 100% SafeNeedle vs cannula for filler in high-risk facial regions. What the occlusion data, arterial penetration s
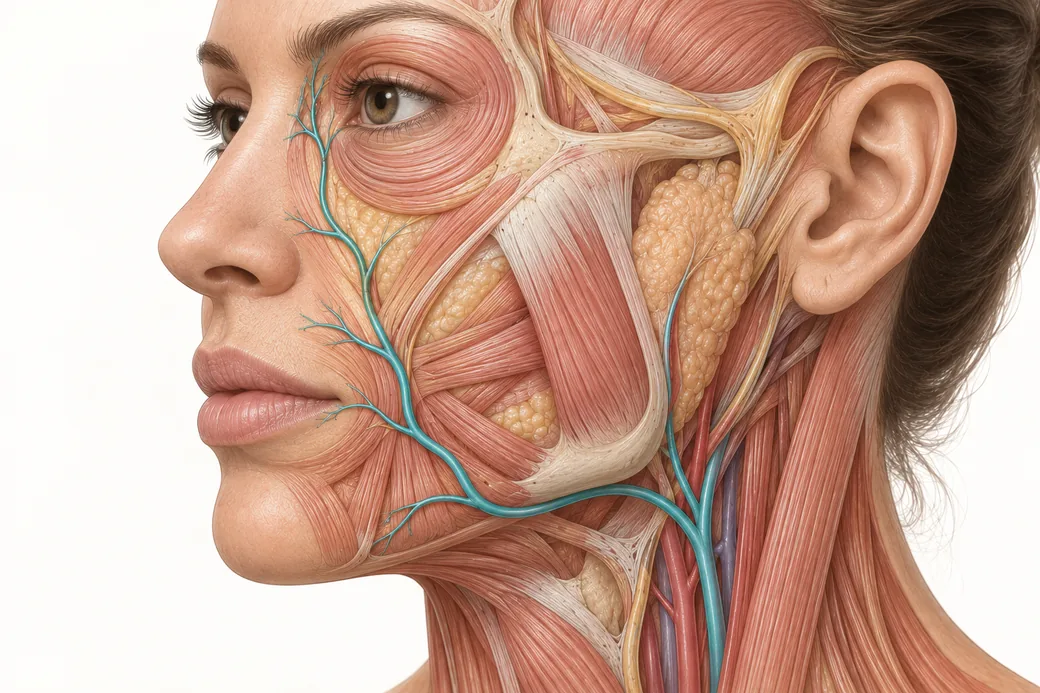 Thinking in Layers: Depth as the Second Axis of the Vascular MapFacial layers explained for injectors — the five-layer model, which layer each facial artery occupies, an
 Aspirate, Low Pressure, Small Volumes, Stop Early: Four Habits That Reduce Vascular ComplicationsAspirate, low pressure, small volumes, stop early. What the evidence actually supports for each habit — i
 Retrograde Embolisation: How Injection Pressure Sends Filler Where You Didn't Put ItHow retrograde embolisation works: the injection pressures involved, the volumes that matter, how filler
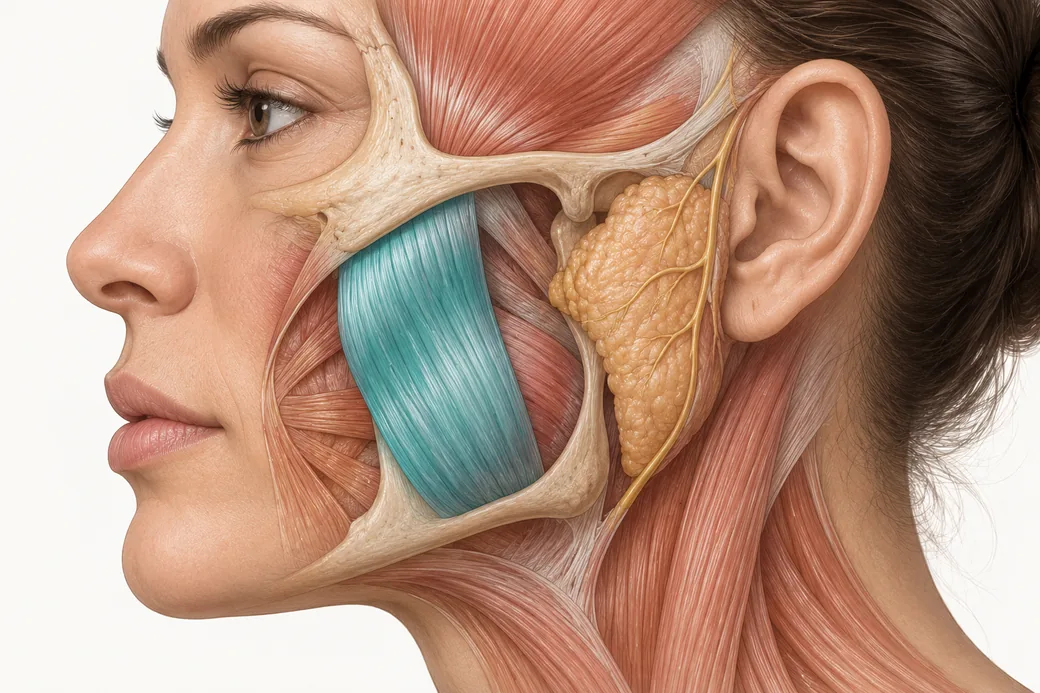 The Bizygomatic-to-Bigonial Ratio: Assessing the Lower-Face Slimming CandidateUse the bizygomatic to bigonial ratio plus a clench-release-palpate exam to select lower-face slimming ca
 Treat Movement, Not Dots — Dynamic Facial Assessment for NeurotoxinDynamic facial assessment for neurotoxin is what a chart cannot give you: reading movement, vectors and a
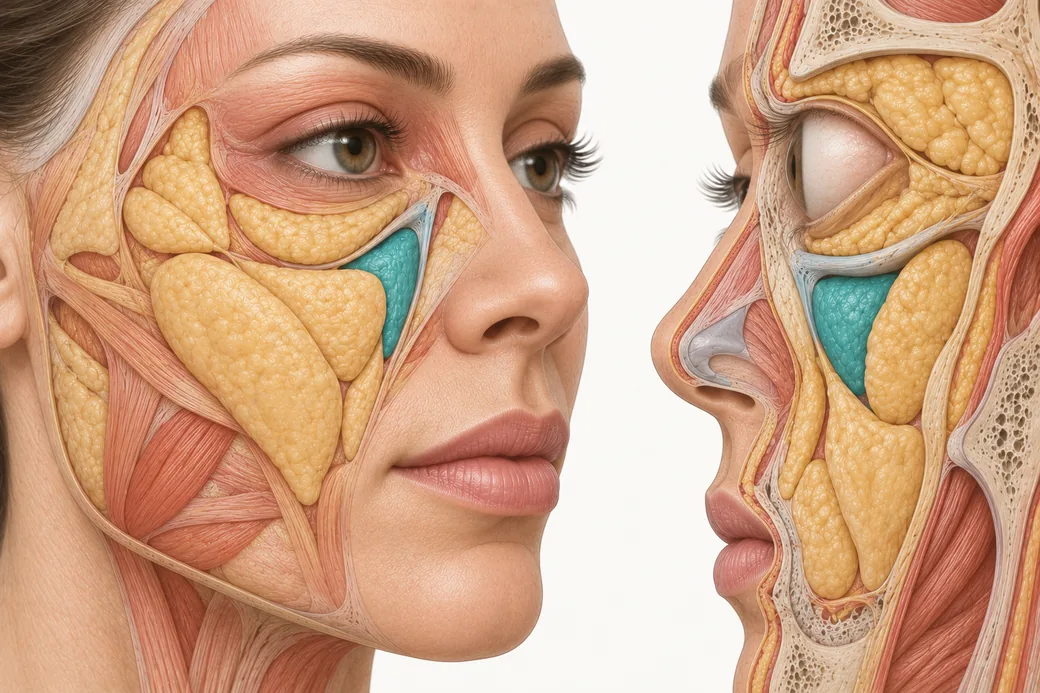 The Four-Layer Model of Facial Aging: Reading a Face from Bone to SkinThe four-layer model of facial aging — bone, fat, muscle and ligament, skin — used as a deep-to-superfici
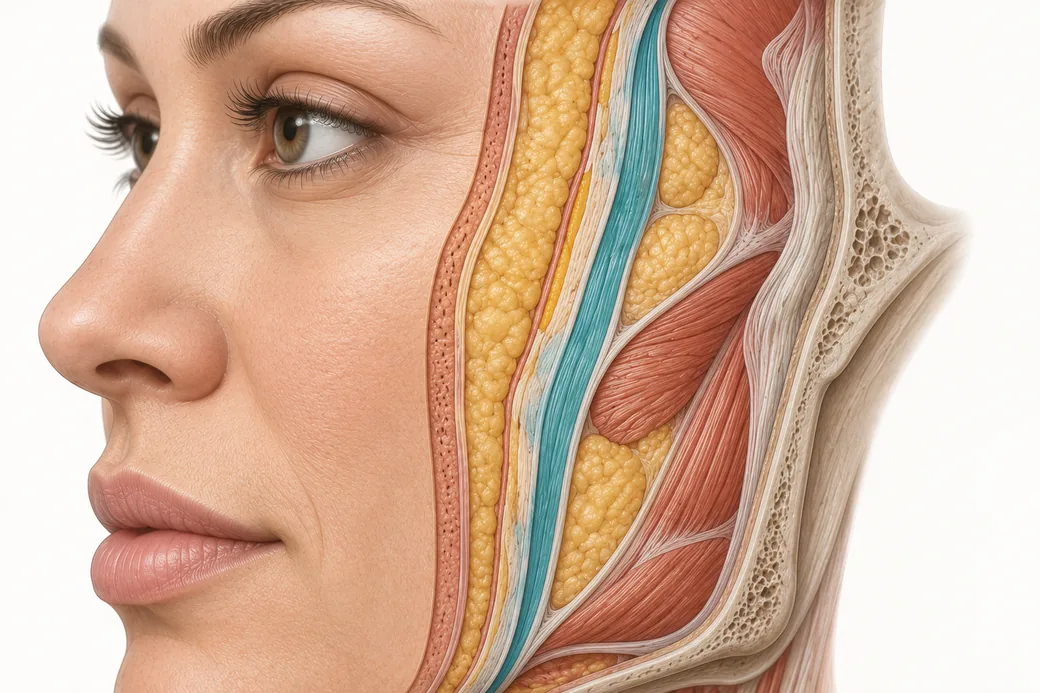 The Product Belongs in the Plane of the ProblemInjection plane selection, stated as one rule: the product belongs in the plane of the problem. The two f
 Anatomy in Motion: Facial Palpation and Expression AssessmentFacial palpation assessment and expression reading for injectors — what your hands find that a diagram ca
 Brow Ptosis vs Eyelid Ptosis: Two Toxin Complications, Two Different MusclesBrow ptosis and true eyelid ptosis look alike to the patient but arise from different muscles. The fronta
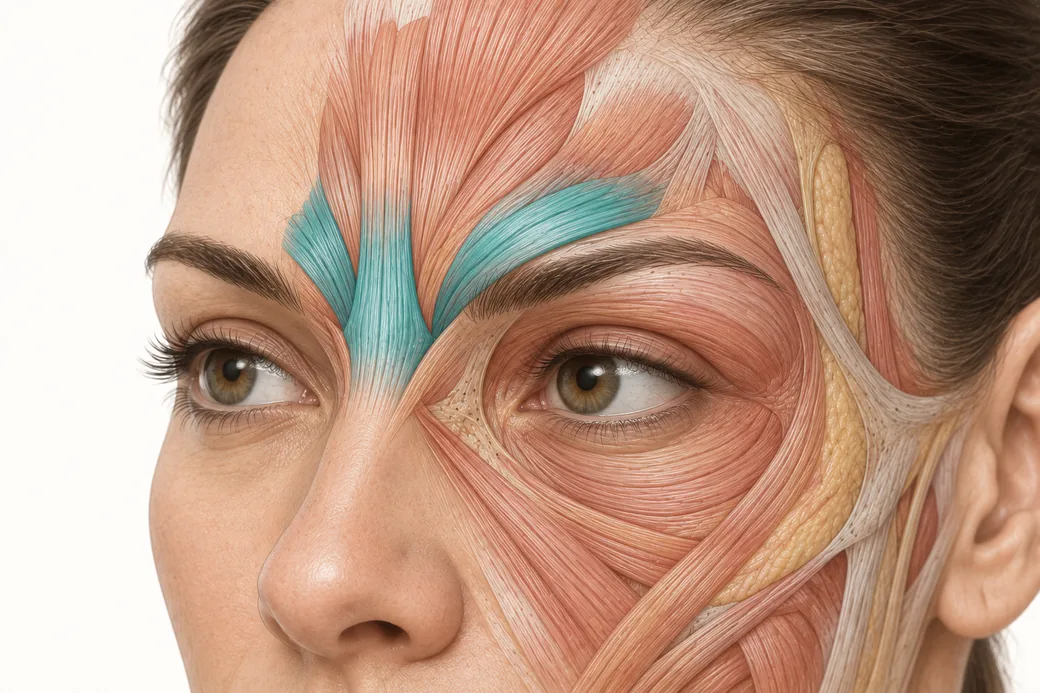 One Muscle, Two Depths: The Corrugator Injection Depth Rule and the Anatomy Behind ItThe corrugator needs two injection depths, not one. The anatomy of the medial head, the lateral tail, fro
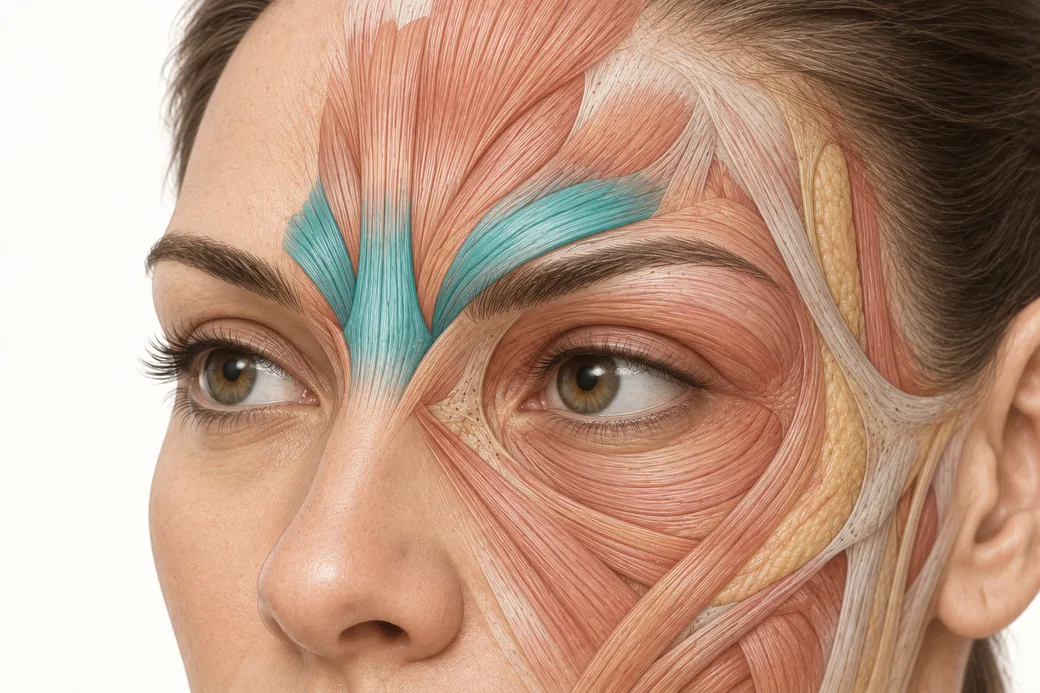 Agonist and Antagonist — Why the Frontalis and Glabellar Complex Are Planned as One PairThe frontalis and glabellar complex are an opposed muscle pair. Why treating one without the other unbala
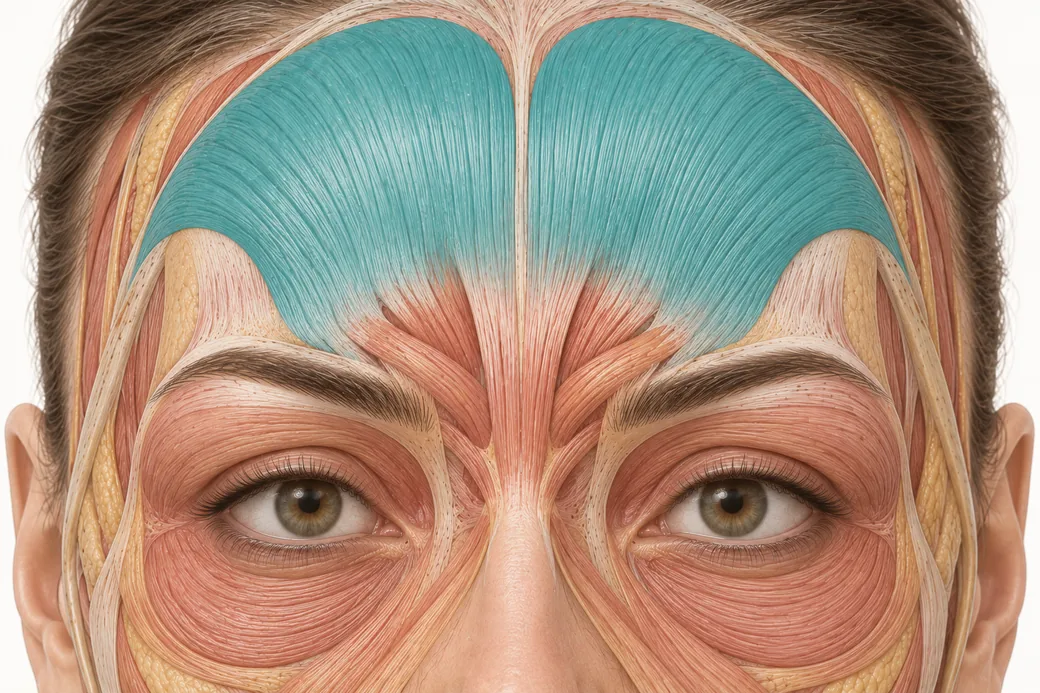 Spock Brow After Botox — The Compensation Pattern Behind an Untreated Lateral FrontalisA spock brow after botox is compensation, not misplacement. How untreated lateral frontalis fibres recrui
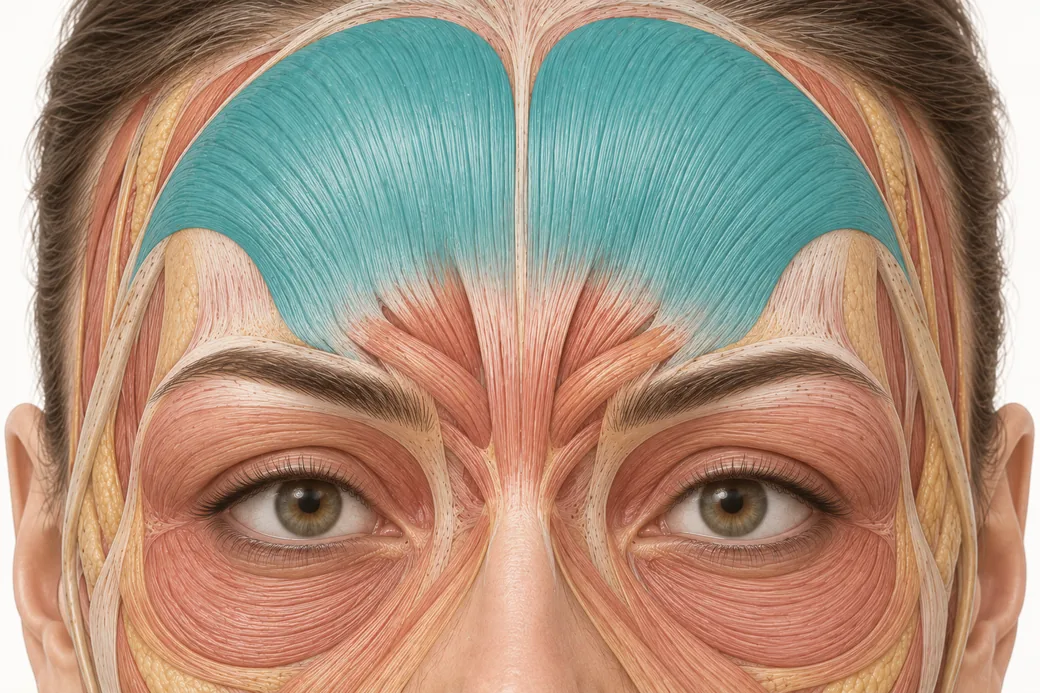 The Line of Convergence — The Frontalis Landmark That Decides Whether You Lift a Brow or Drop ItThe line of convergence is where frontalis movement reverses direction. How to identify it dynamically, a
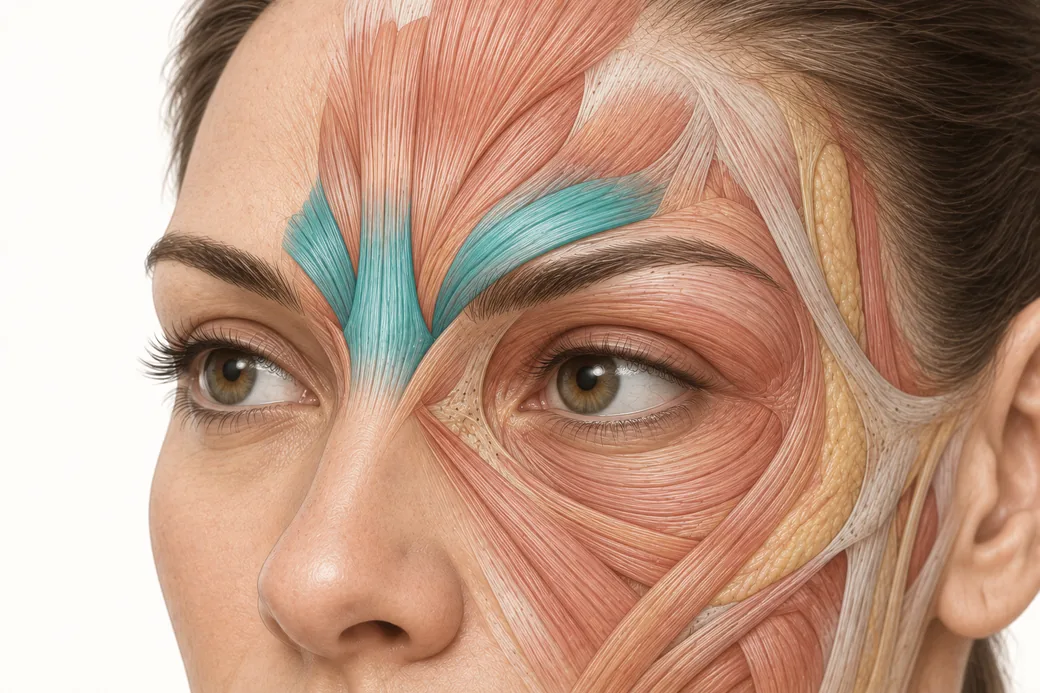 Horizontal or Vertical Tails — Corrugator Muscle Variation, and Why Two Injectors Can Both Be RightCorrugator muscle variation explains why two injectors treat the same glabella differently, and how to re
 Depressor Anguli Oris, DLI and Mentalis — Three Overlapping Muscles, Millimetres ApartDepressor anguli oris anatomy is a depth problem, not a map problem. The DAO, DLI and mentalis overlap in
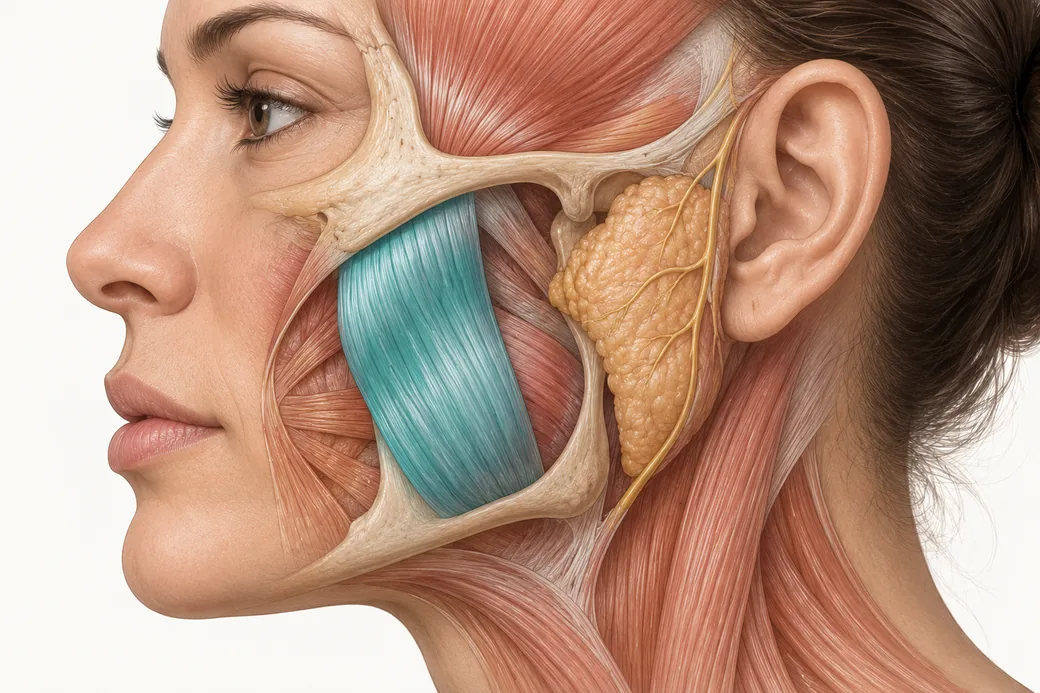 Two Clocks, One Muscle: The Masseter Botox Results TimelineThe masseter botox results timeline runs on two clocks — symptom relief in 1–2 weeks, visible facial slim
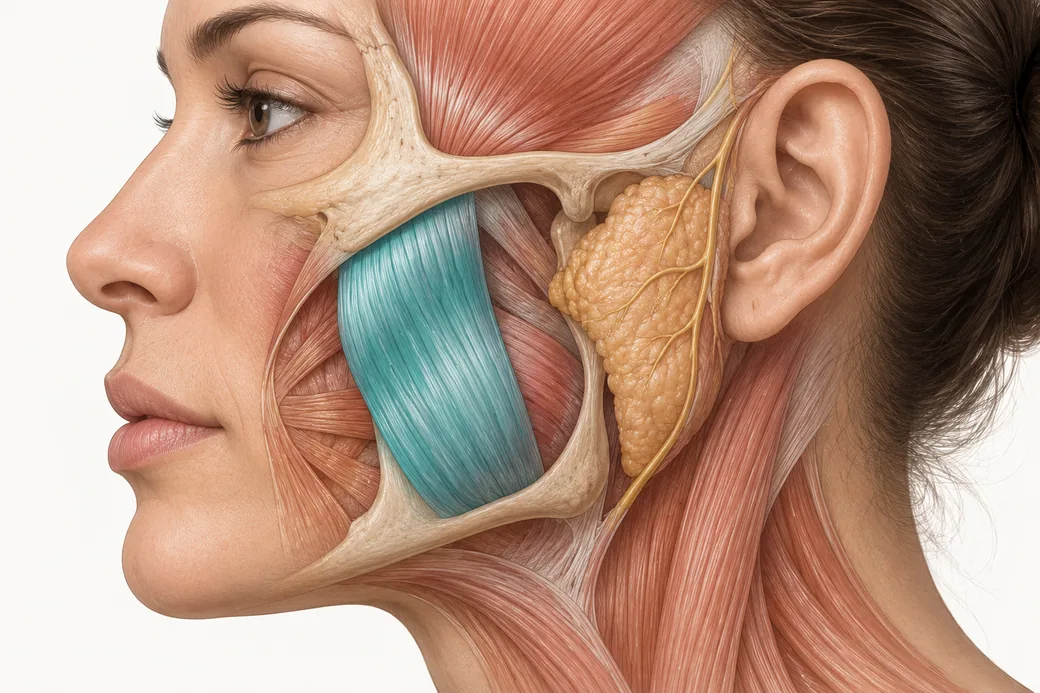 Mapping the Masseter: Borders, the Tragus-to-Commissure Line, and What Sits Above ItThe masseter injection safe zone in full — layered anatomy, the tragus-to-commissure line, anterior and p
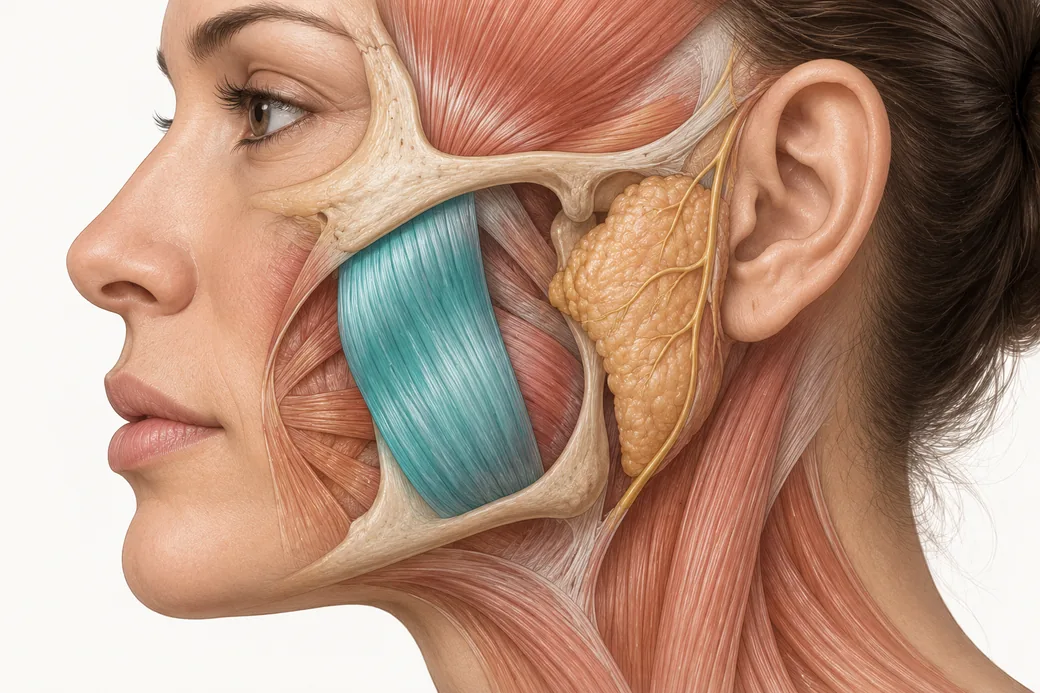 Who Should Not Be Slimmed: Jowls, Skin Laxity and the Masseter Atrophy Trade-OffMasseter botox and jowls — the muscle provides structural bulk, so atrophy can worsen laxity. Candidate s
 Less Forgiving by Design — Lower Face Neurotoxin and the Real Margin for ErrorLower face neurotoxin is less forgiving for structural reasons. What the margin for error actually is bel
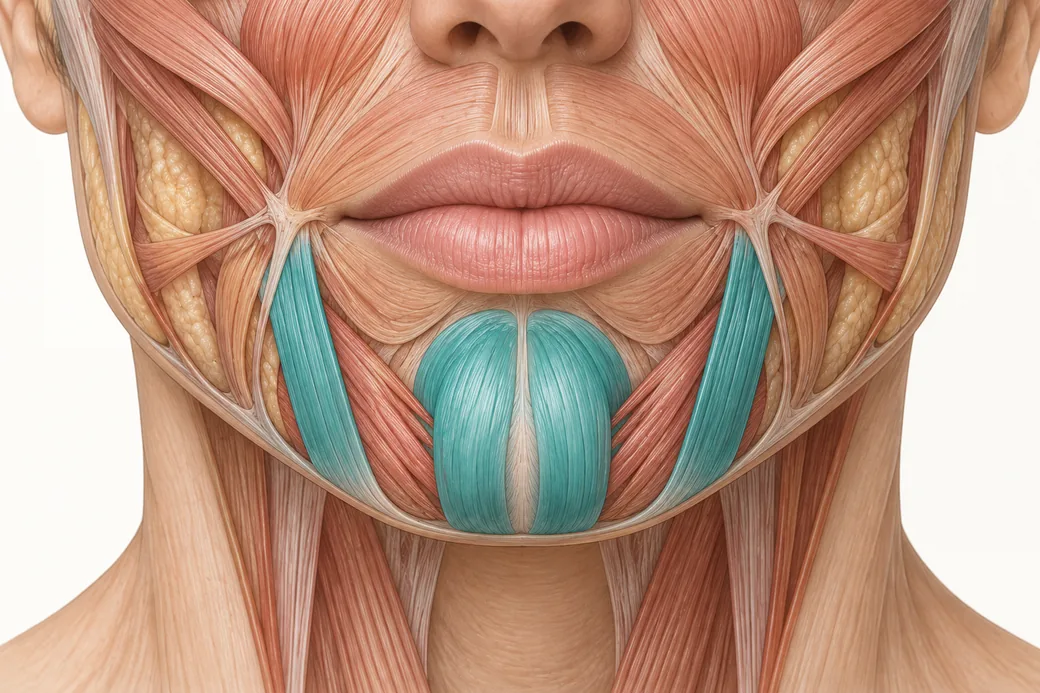
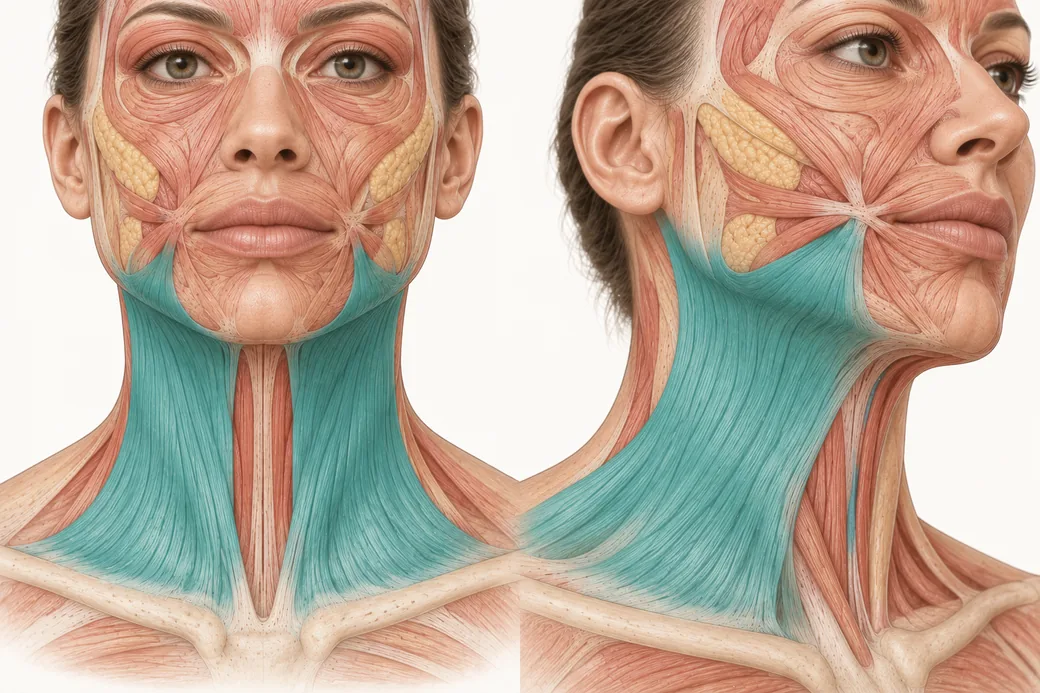 The Platysma Nefertiti Lift — From Clavicle to ModiolusThe platysma runs from the clavicle to the mandible, lower lip and modiolus. The anatomy behind the Nefer
 Most Neurotoxin Complications Are Diffusion, Not Misplacement — Rethinking Root CauseMost neurotoxin complications come from diffusion into an adjacent muscle, not from injecting the wrong s
 The Crow's Feet Trap — How Chasing Lateral Cheek Lines Reaches the ZygomaticusA zygomaticus botox complication after crow's feet treatment has one usual cause — chasing lateral cheek
 The Expected Filler Injection Response — Building the Baseline That Lets You Recognize IschemiaThe expected filler injection response — erythema, edema, ecchymosis — and how a trained normal baseline
 The Golden Triangle — Why the Filler Deposit Site Isn't Where You Put the Needle InThe filler deposit site sits at the needle tip, not the entry point — about half an inch away, further wi
 Immediate, Early and Late — The Three Windows of Vascular Occlusion OnsetVascular occlusion onset is not one moment. Organize the picture into immediate, early and late windows —
 The Five-Step Perfusion Exam — Reading the Signs of Vascular Occlusion in SequenceThe signs of vascular occlusion are only reliable inside a fixed sequence: scan, pain trajectory, capilla
 Compression Occlusion vs Vascular Occlusion — and Why You Can Have BothCompression occlusion and intravascular occlusion are different mechanisms that coexist. Why volume per p
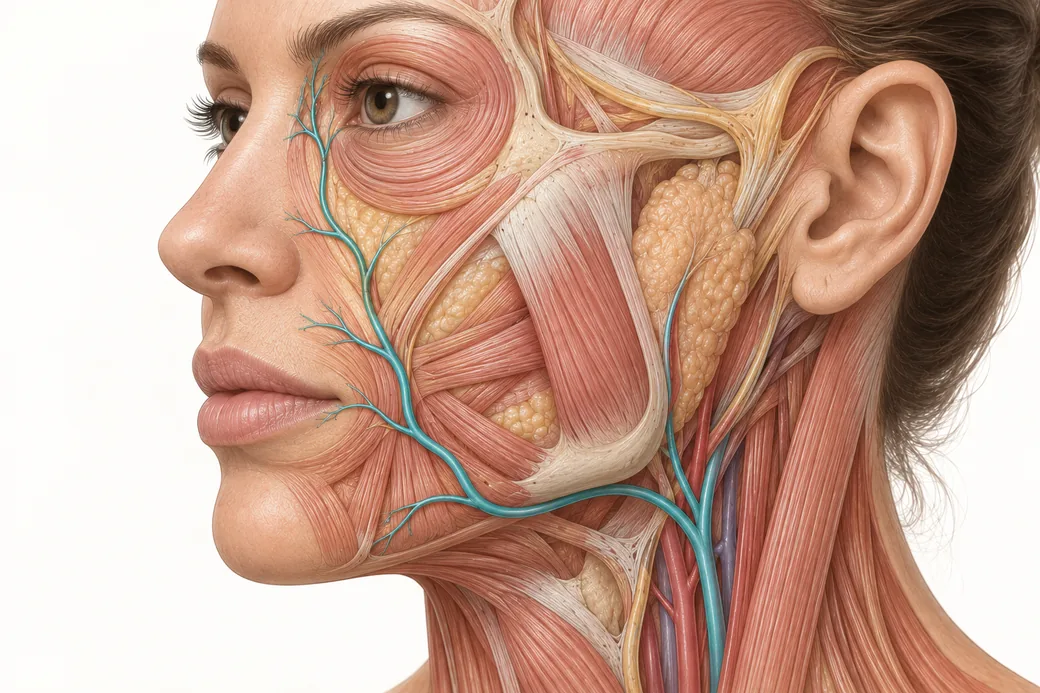 Read the Vascular Territory, Not the Injection Point — Why Findings Appear Away From the DepositOcclusion findings appear in the vascular territory, not at the puncture. Scan downstream, know why infla
 The Asymmetry Tell: When Vascular Occlusion Asymmetry Matches Your Injection PatternVascular occlusion asymmetry is diagnostic data. Why sparing of untreated tissue argues against generalis
 Read the Sequence, Not the Snapshot: Occlusion Morphologic Progression in the Upper LipOcclusion morphologic progression in one site — dusky spot, blanching, mottling, spread, reticular change
 What Hyaluronidase Actually Does: Enzyme Mechanism for InjectorsHyaluronidase mechanism of action for injectors: cross-link cleavage, tissue permeability, passive vessel
 What Hyaluronidase Cannot Do: Non-HA Filler ComplicationsHyaluronidase does not reverse CaHA or PLLA. Why Michelle Langston still floods the territory, and why a
 When Is the Emergency Actually Over? Vascular Occlusion Recovery and the Re-Injection WindowVascular occlusion recovery is measured in weeks, not minutes. Daily rechecks, retreating an unresolved c
 Routine, Urgent or Emergency: Triaging the Post-Filler Phone CallPost-filler phone call triage in three tiers — routine, urgent, emergency. Michelle Langston's framework
 The Handoff: What a Competent Emergency Transfer Looks LikeFiller complication emergency transfer, done properly: never send the patient alone, keep treating while
 On-Label Reconstitution Across the US Neurotoxins — A Reference Table for InjectorsA complete on-label neurotoxin reconstitution chart for Botox, Dysport, Xeomin, Jeuveau and Daxxify — via
 Bacteriostatic vs Preservative-Free Saline — What the Benzyl Alcohol Actually DoesBacteriostatic saline for neurotoxin reconstitution is off-label but well studied. What benzyl alcohol do
 Concentration as a Clinical Instrument — How Dilution Governs DiffusionNeurotoxin dilution and diffusion, worked as a decision. When to choose a tighter concentration, when to
 Why a Unit of Botox Is Not a Unit of DysportBotox units vs Dysport units are not the same measure. Units are defined by each manufacturer's own poten
 Insulin, 0.5 mL and 1 mL Syringes — Why Three Injectors Drawing "the Same Dose" See Three Different MarksUsing an insulin syringe for neurotoxin dosing means reading insulin units, not toxin units. How graduati
 Dose Equals Duration — The Principle That Predicts How Long a Neurotoxin Complication Will LastDose equals duration is the principle that lets clinicians forecast how long a neurotoxin complication wi
 Extrapolating Doses to Off-Label Muscles — A Reasoning FrameworkOff-label neurotoxin dosing has no reference table. Dr. Chris Croley's inference method — size, density,
 The Collagen Stimulator Landscape: Skin Boosters vs Biostimulators vs Fillers, ComparedSkin boosters vs biostimulators vs fillers, compared by goal, plane, onset and failure mode — a four-cate
 Choose by Tissue Diagnosis, Not by Trend: A Collagen Biostimulator Decision TreeA collagen biostimulator decision tree for injectors — four tissue findings, four products, and the five-
 The Biostimulator Results Timeline: Why Three Months, and How to Set It at ConsultationThe biostimulator results timeline injectors should set at consultation: why day-zero fullness is water,
 Combining Filler and Biostimulator in the Lower Face: Lift With One, Treat Quality With the OtherCombining filler and biostimulator in the lower face — which products pair, which planes they take, and w
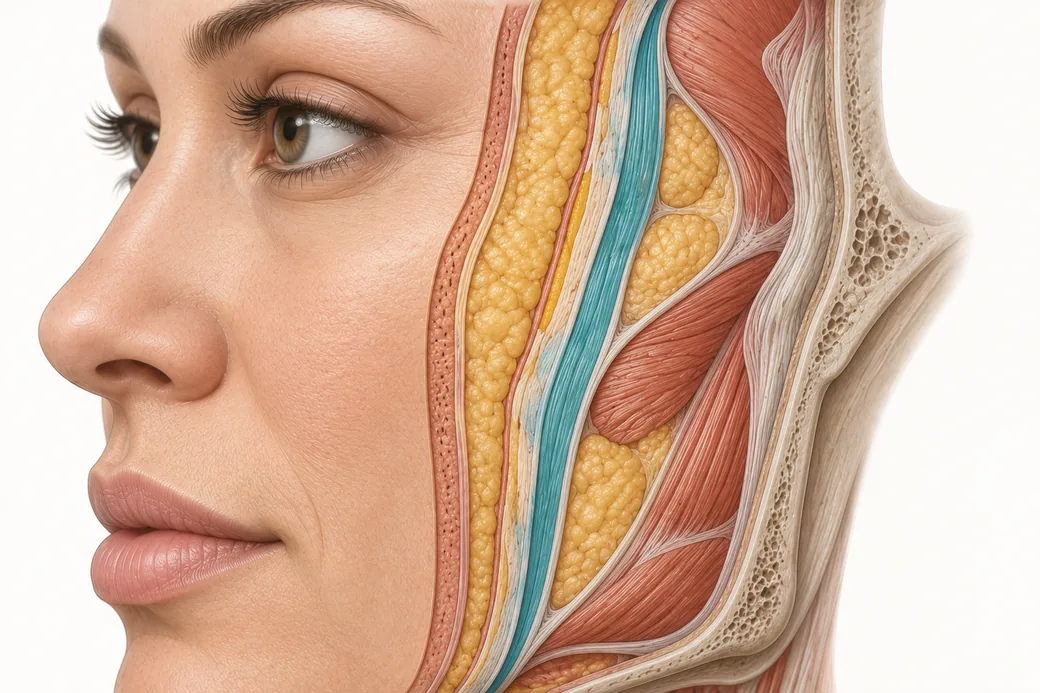 The Layered Treatment Recovery Timeline: When Each Outcome Becomes AssessableA layered treatment recovery timeline from day 0 to month 6 — what is assessable in each window, what is
 PLLA Aftercare and the 5-5-5 Massage Rule: What the Label Says and What the Evidence ShowsPLLA aftercare for injectors: what current Sculptra labelling says about the 5-5-5 massage rule, why nodu
 Dilution Changes Behaviour: Why Hyperdilute CaHA Diffuses Instead of VolumisingHyperdilute CaHA for injectors: how dilution ratio turns Radiesse from a volumiser into a diffuse biostim
 Waiting Intervals After Toxin or Filler Before Any Skin TreatmentThe waiting interval after toxin or filler before microneedling or a peel — what the drug labels actually
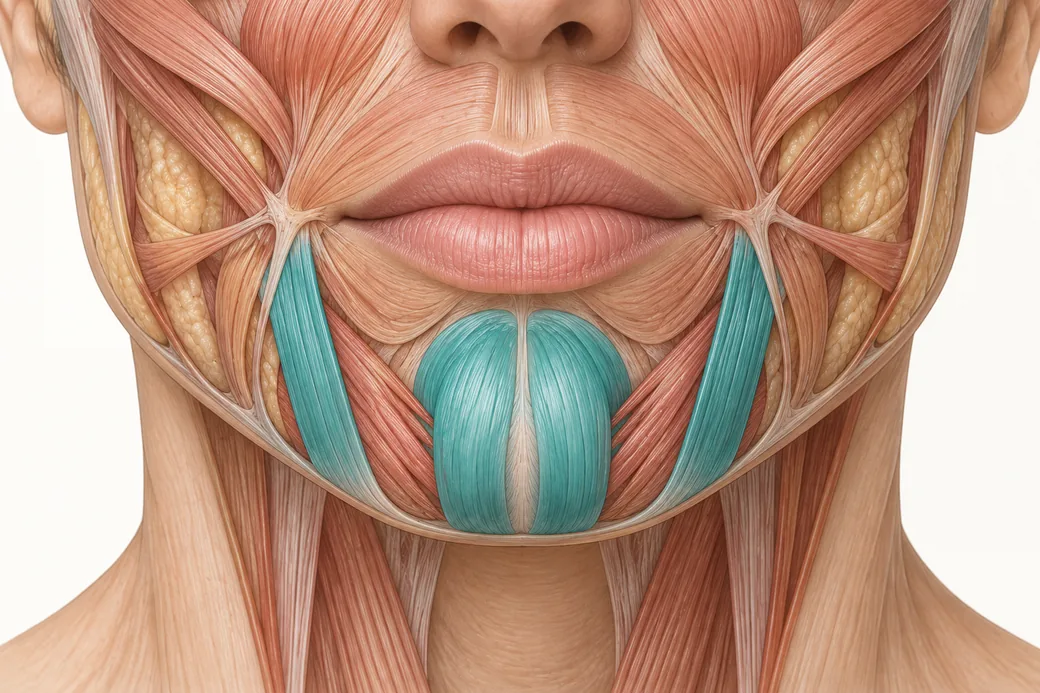 Matching Treatments to Tissue Level: Injectables, Microneedling and PeelsMatching treatments to tissue level — which findings live in the epidermis, dermis, fat compartments or m
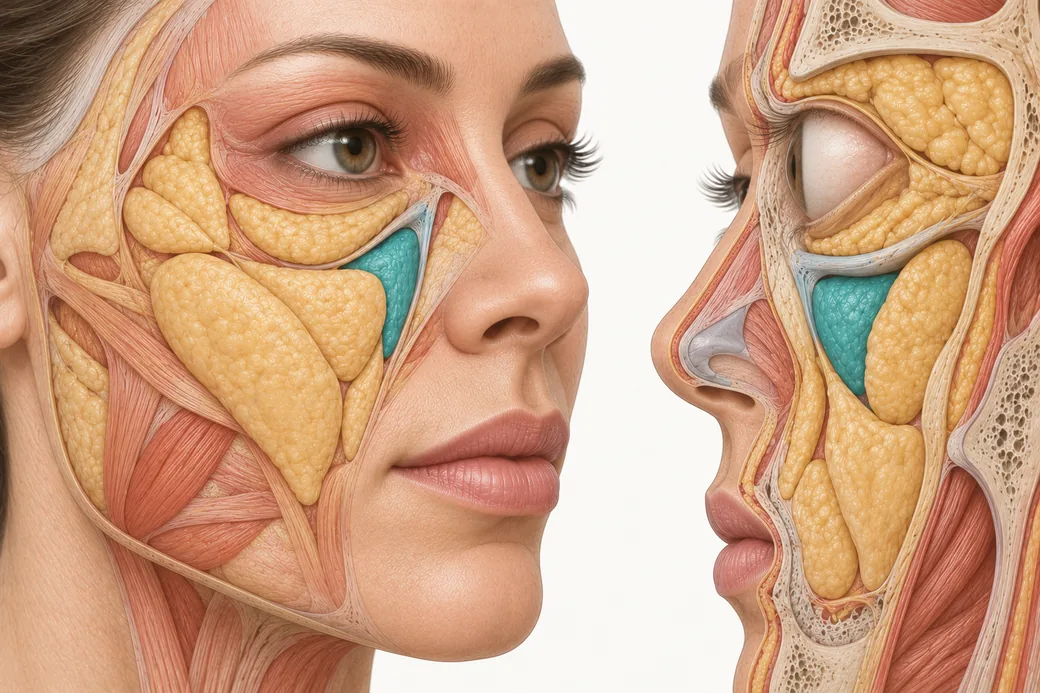 G Prime Filler Selection and the Fat Compartments: Firm or Soft, and Where It GoesWhat G prime filler ratings really measure, why cross-brand comparisons mislead, how to match firm and so
 Standardized Clinical Photography and Documentation for Multi-Modality PlansStandardized clinical photography for layered aesthetic plans — the variables to fix, the view set, skin-
 Single Spin vs Double Spin PRP: What Actually Changes in the TubeSingle spin vs double spin PRP compared for clinicians — what the second spin concentrates, why volume co
 Leukocyte-Rich vs Leukocyte-Poor PRP: Matching Cell Content to the IndicationLeukocyte-rich vs leukocyte-poor PRP explained for clinicians — the cytokine data, the PAW, DEPA and Doha
 Diagnose Before You Treat: The Hair Loss Workup That Must Precede PRPThe hair loss workup before PRP, step by step — onset history, pattern recognition, trichoscopy, category
 Sequencing PRP with Microneedling and Laser: Recovery and Remodelling SupportSequencing PRP with microneedling and laser — same-session versus staged delivery, what the recovery evid
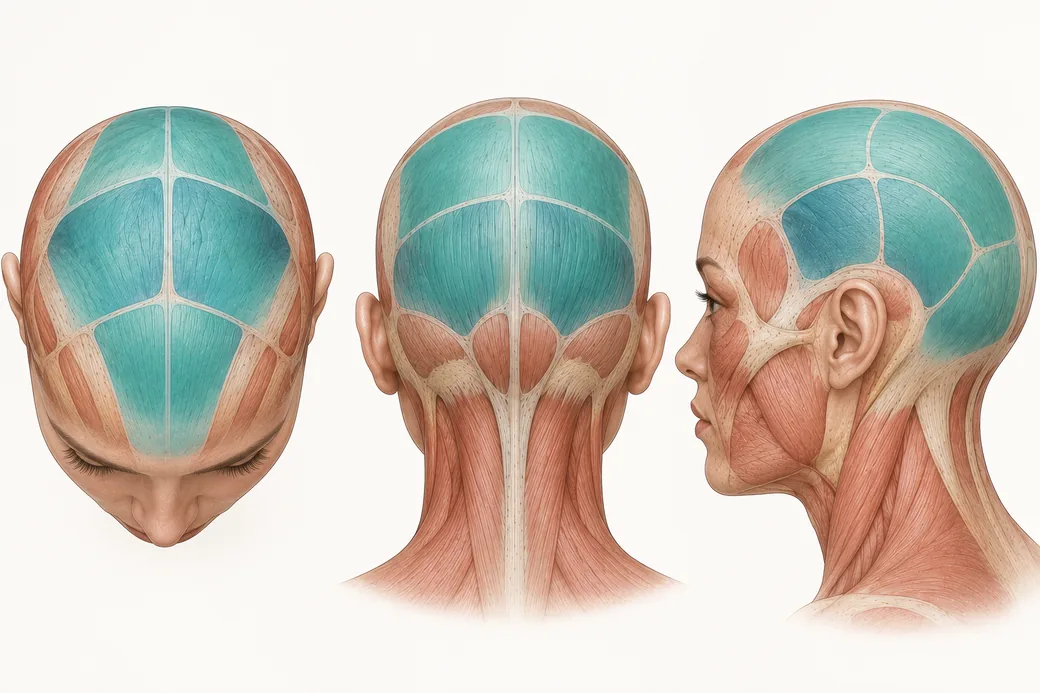 Scalp Mapping for PRP: Injection Patterns That Guarantee CoverageA PRP scalp injection pattern you can prove — linear front-to-back passes, retrograde technique, circular
 Why PRP Protocols Fail: Prep Inconsistency, Equipment Drift and the Dehydrated PatientWhy PRP protocols fail before the needle ever reaches the scalp — tourniquet time, anticoagulant ratio, R
 The Clotting Clock: How the PRF Working Window Reshapes Your RoomThe PRF working window is minutes, not hours. How the clotting clock rewrites room layout, staffing, sche
 Choosing by Clinical Job: A PRP or PRF Decision FrameworkA PRP or PRF decision framework for injectors, organised by the clinical job you need done — release curv
 PRP with Microneedling: Why PRF Can't Take Its PlacePRP with microneedling works because the material stays liquid, spreads and glides. The materials case fo
 Benzodiazepine or Clonidine? Choosing an Oral Anxiolytic for the Long Aesthetic AppointmentBenzodiazepine vs clonidine for pre-procedure anxiolysis — the mechanisms, the respiratory and scheduling
 Sublingual Ketamine in the Aesthetic Suite: Where It Fits, and What It Costs YouSublingual ketamine is the wrong tool for toxin and the right one for higher-discomfort work. The pharmac
 Calculating the Maximum Lidocaine Dose: The Arithmetic Every Injector Should Do ColdHow to calculate a maximum lidocaine dose from weight and concentration, with worked examples — and why t
 Why Lidocaine and Not Bupivacaine or Ropivacaine in the OfficeLidocaine vs bupivacaine and ropivacaine for office blocks: the margin of safety in milligrams, and the c
 Recognising Local Anesthetic Systemic Toxicity Before the Cardiac SignsLocal anesthetic systemic toxicity announces itself in the nervous system first. The prodrome, the facial
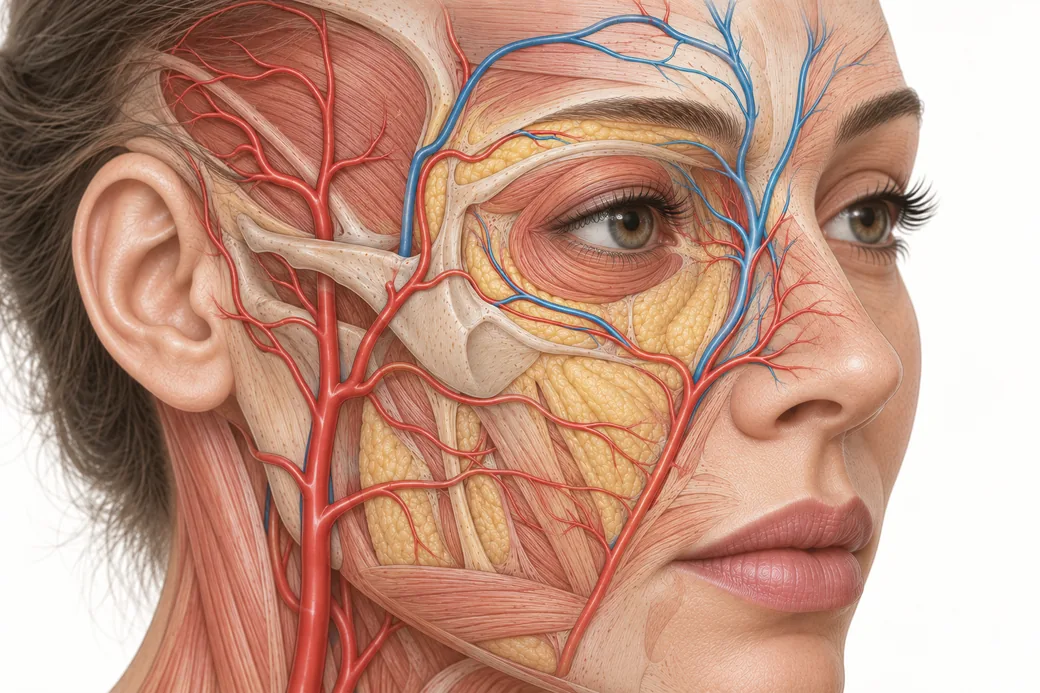 The Four Office Blocks and Their Gaps: Supraorbital, Infraorbital, Mental and the Greater Auricular ExceptionFacial nerve blocks an aesthetic practice can actually place — supraorbital, infraorbital and mental tech
 Nitrous Oxide in the Aesthetic Practice: Self-Titration, Contraindications and Same-Day DrivingNitrous oxide in aesthetic practice is the one non-controlled, self-limiting option. Titration range, con
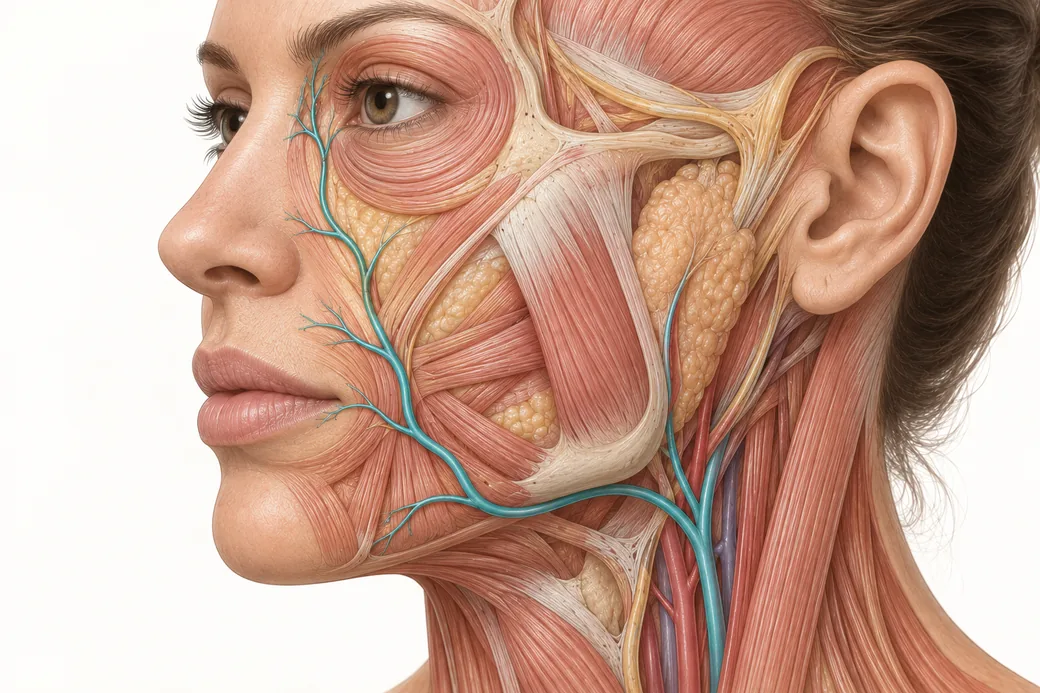 The Trigeminal Nerve Map: V1, V2, V3 and What Each Territory Buys YouA working trigeminal nerve map for injectors — what V1, V2 and V3 each cover, where the boundaries fail,
 Mono, Screw and Cog — Matching the PDO Thread Family to the Clinical JobPDO thread types explained by mechanism, not by brand. How mono, screw and cog threads differ in what the
 The Two-Phase PDO Thread Timeline — and the Mid-Course Drop Nobody Warns Patients AboutThe PDO thread lift timeline runs two clocks — suture absorption and collagen response. The gap between t
 Who Is Not a Thread Candidate — Patient Selection That Protects Your OutcomesThread lift patient selection by failure mechanism — severe laxity, heavy tissue, crepey skin, fat hernia
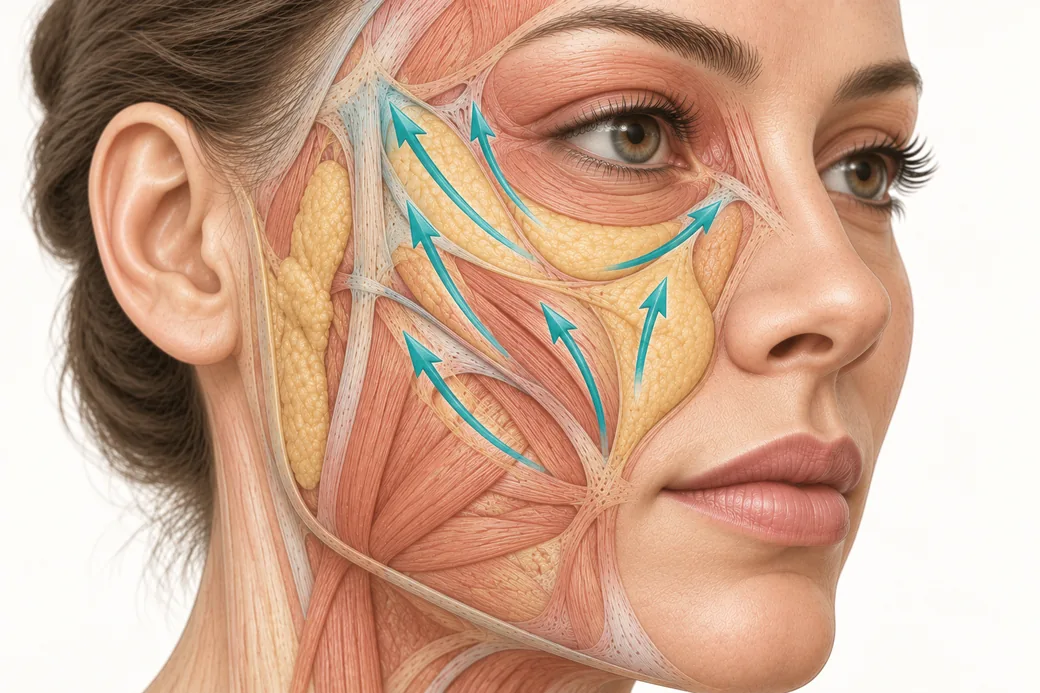 Vector Planning for the Midface — Why Direction Decides the ResultThread lift vector planning for the midface: why direction decides the result, how the V-configuration ma
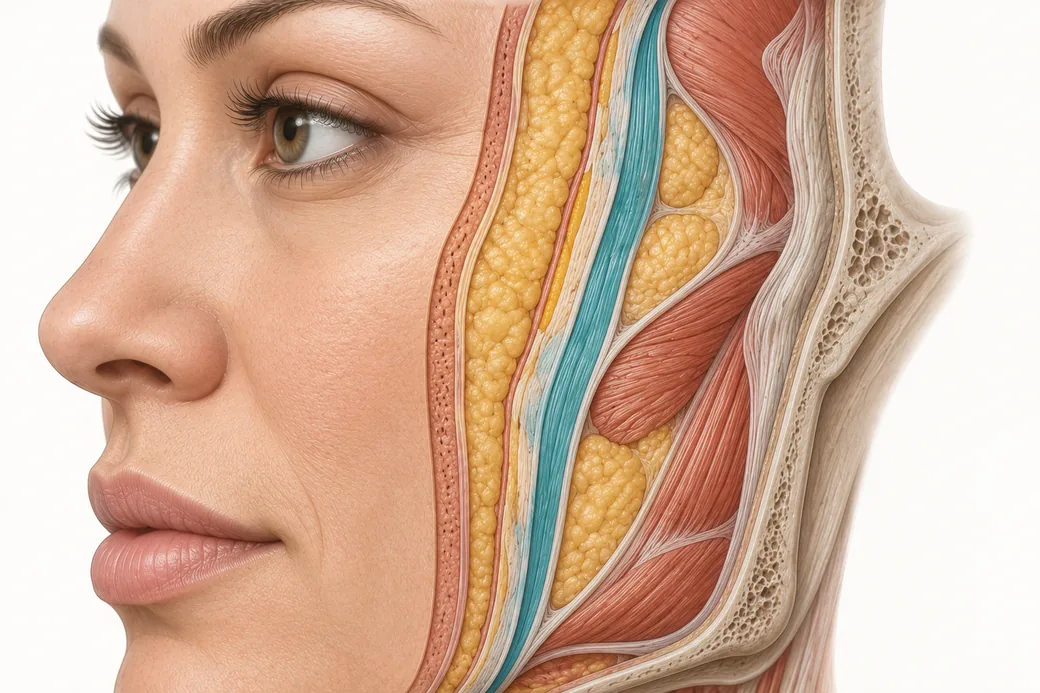 Finding the Plane by Feel — What Resistance Is Telling You During Thread PlacementThe correct PDO thread insertion plane is found by feel, not by depth. Resistance means wrong plane; glid
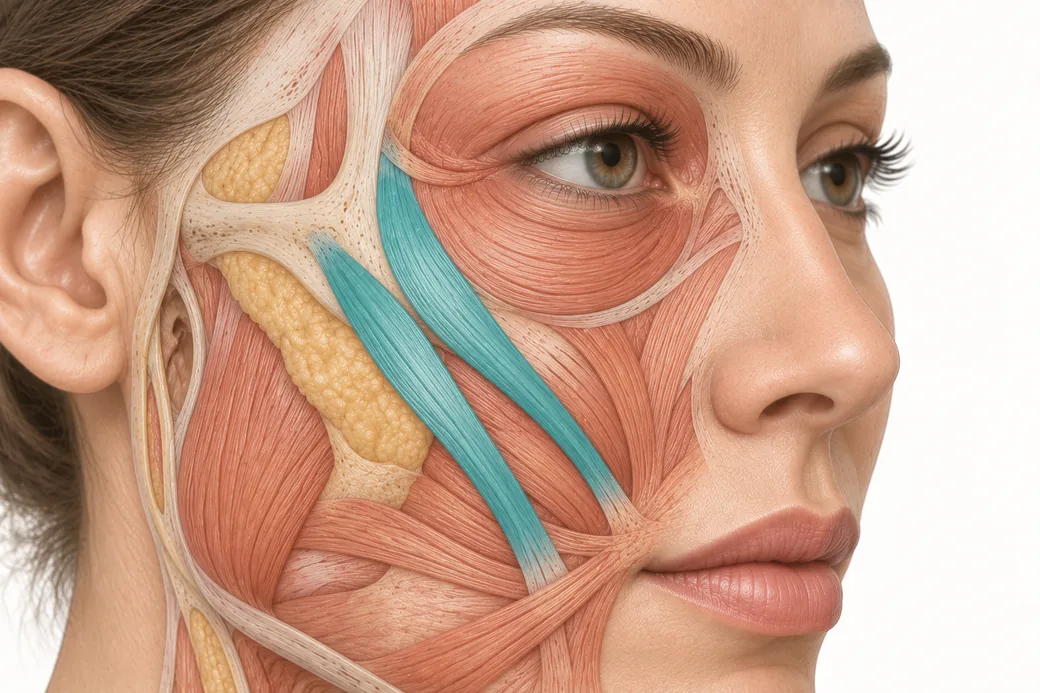 Crowded Vectors and Over-Correction — The Two Layout Errors That Cause DimplingThread lift dimpling has two causes — crowded overlapping vectors and over-correction. They look alike, a
 How Deoxycholic Acid Works: Adipocytolysis, Inflammatory Clearance, and Why Swelling Is the TreatmentHow deoxycholic acid causes adipocytolysis, why the inflammatory swelling that follows is the clearance m
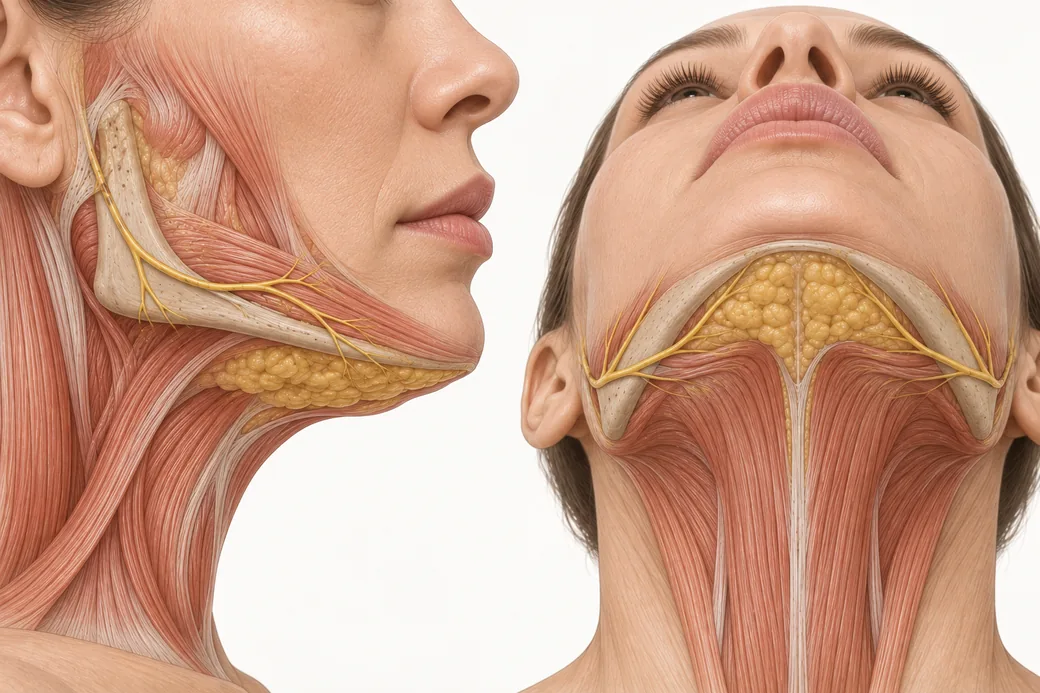 The Submental Pinch Test: Distinguishing Fat from Skin Laxity Before You Open a VialThe submental pinch test separates treatable fat from skin laxity. Maritza Mejia's thumb-and-index techni
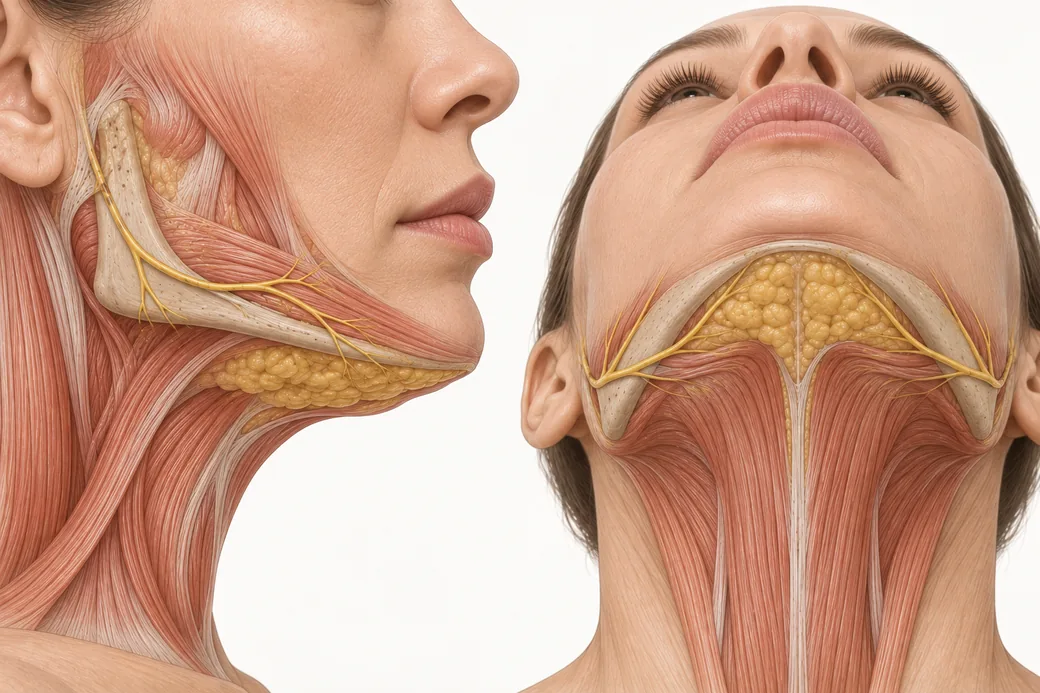 Submental Anatomy for Deoxycholic Acid: Compartments, the Submandibular Extension and the Marginal Mandibular NerveThe safety anatomy of the neck for injectors — preplatysmal versus subplatysmal fat, the submandibular ex
 Dynamic Neck Assessment: Resting, Smiling, Flexion and ExtensionA four-position neck examination for injectors — what rest, animation, flexion and extension each reveal
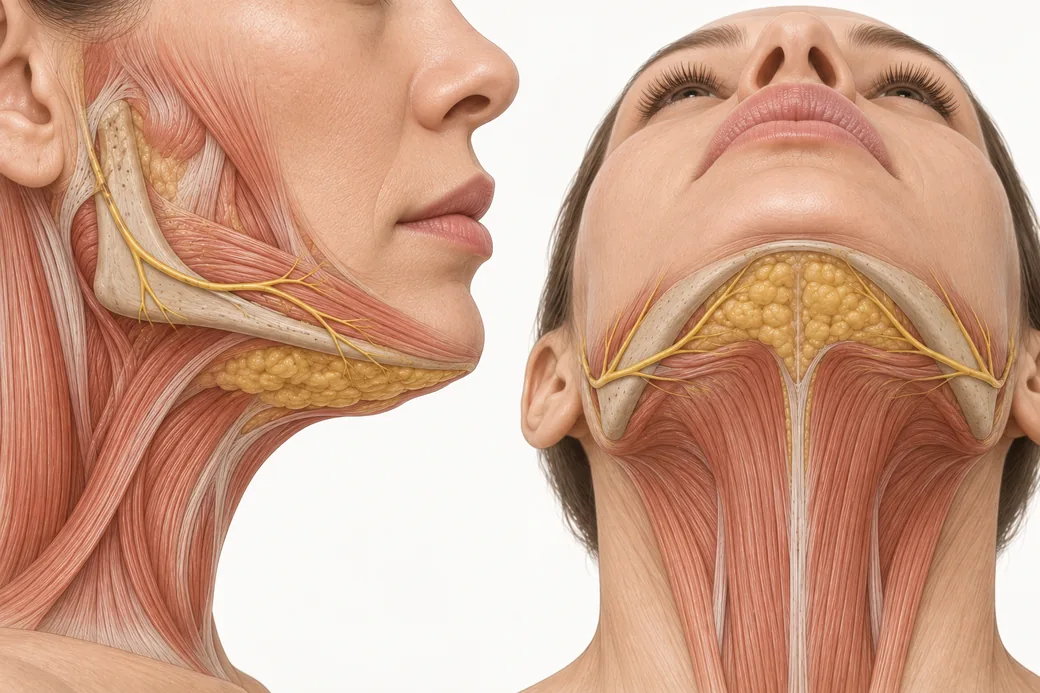 Don't Memorise Doses: Why Submental Treatment Volume Is Driven by the Compartment, Not the ChartKybella dosing is expressed per square centimetre, not per patient. How to derive treatment volume from t
 Chronic Migraine On-Label Criteria: Deciding Which Patients Actually QualifyChronic migraine criteria decide who you can treat on-label. The label wording, the ICHD-3 definition, th
 Confirm the Diagnosis First: Secondary-Headache Red Flags Before You InjectSecondary headache red flags decide whether a migraine patient gets injected or referred. The SNNOOP10 fr
 The PREEMPT Protocol: Why Fixed-Site, Fixed-Dose Was the Trial Design, and What It Means in PracticeThe PREEMPT protocol is fixed-site, fixed-dose for a reason. What the trial design was, why the label is
 Migraine Treatment Outcome Measures vs Aesthetic Endpoints: Two Assessment FrameworksMigraine treatment outcome measures are disease burden, not movement. The four domains to record, the res
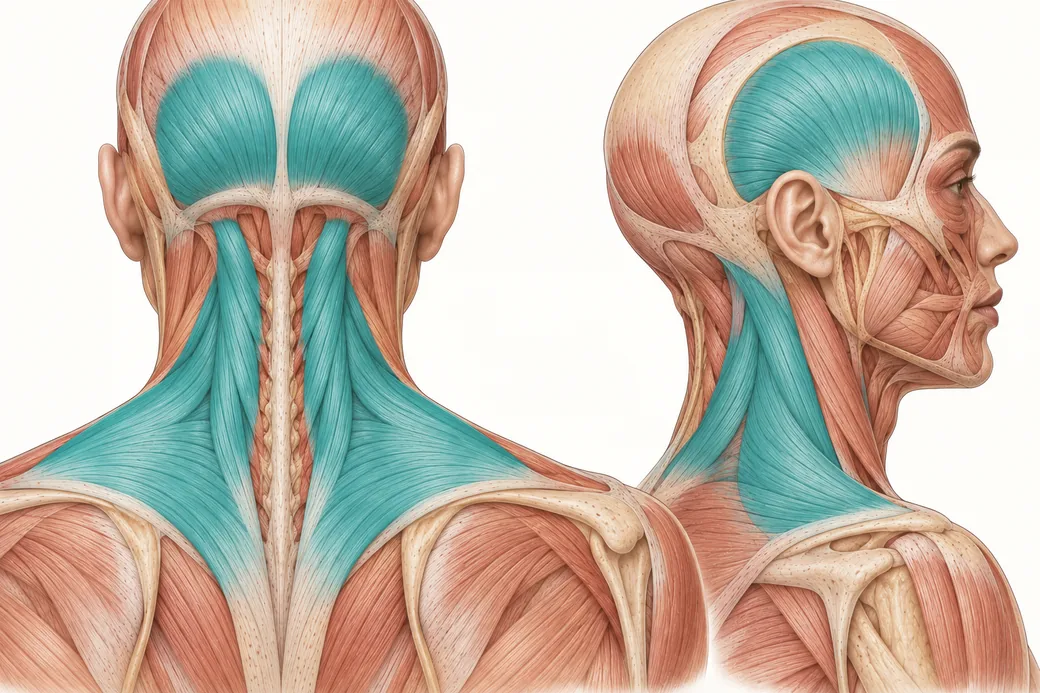 Trapezius and Occipitalis Botox Injections: The Posterior Fields Aesthetic Injectors Never LearnTrapezius and occipitalis botox injections sit outside every aesthetic injector's training. The anatomy,
Everything here is drawn from what Empire faculty teach. The reasoning is published; the technique is taught hands-on, on live patients, with an instructor beside you.
Claim $200 OFF Any In-Person Course
Hands-on, CME-accredited training with live patients. Tell us where to send your discount.