







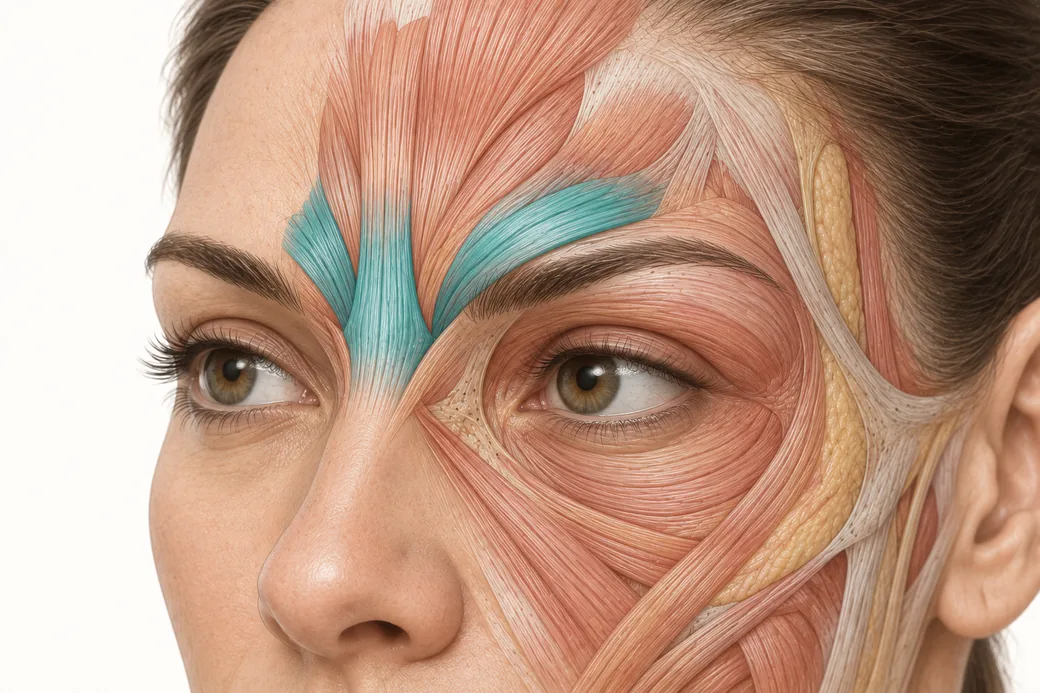
Corrugator injection depth is usually taught as a single number. Deep, intramuscular, against bone — one muscle, one plane, three or five points depending on whose protocol you learned. That instruction is correct for part of the muscle and actively wrong for the rest of it, and the consequence of applying it uniformly is not a suboptimal result. It is the opposite of the result you were treating for.
"This is a very big question I get asked all the time," says Melissa Pulcini-Buttine, PA. "Why is the lateral part of the corrugator more superficial?"
The answer is one of the cleanest illustrations in facial anatomy of a principle that governs neurotoxin practice generally: your injection depth is not determined by the muscle you are targeting. It is determined by what lies between you and it, and by what that structure does.
The corrugator does not stay at one depth
Start with the muscle itself, because the depth change is intrinsic to it.
The corrugator supercilii originates medially, from the frontal bone at the superomedial orbital rim in the region of the superciliary arch. At its origin it is a bony-origin muscle sitting deep, beneath the overlying procerus, frontalis and orbicularis oculi fibres, essentially against the skull.
From there it runs superolaterally and inserts not into bone but into the dermis of the mid-brow. That is its job: it pulls the brow medially and inferiorly, producing the vertical glabellar lines, and it can only do that by attaching to skin.
A muscle that originates on bone and inserts into skin has to travel from the deep plane to the superficial plane somewhere along its length. The corrugator does that as it runs laterally. By the time you are at the lateral tail, the muscle fibres are no longer against the periosteum. They are heading up through the overlying muscle layer toward their cutaneous insertion.
So the first half of the answer is simply anatomical honesty: the medial head and the lateral tail are at different depths because the muscle is at different depths. Melissa teaches it as a two-depth injection for exactly this reason. "The medial part is going to be a deep injection. And then the lateral tail is going to be more superficial."
That alone would justify varying your technique. But it is not the interesting part, and it is not the part that produces complications.
The real reason: what is sitting on top of the lateral tail
The critical structure is the frontalis, and specifically the fact that over the lateral brow, frontalis fibres interdigitate with the corrugator and with orbicularis oculi. The layers in this region are not cleanly stacked. They overlap and interweave.
Melissa's explanation is the mechanism, stated compactly: "If we do a deep injection here we may hit fibres of the frontalis. And the frontalis is an elevator. So if we hit the frontalis here, then we can hit those fibres and then we can cause depression."
Follow the chain carefully, because the failure is counter-intuitive.
- You are treating the corrugator. The corrugator is a depressor of the brow.
- The therapeutic goal of relaxing a depressor is elevation. Melissa states the principle explicitly: "if the job of these muscles is to depress, once we treat them with toxin we'll get elevation."
- You go deep at the lateral tail, because that is what you were taught for the corrugator.
- Deep at the lateral tail is where frontalis fibres sit.
- The frontalis is the only elevator of the brow.
- You have now weakened the elevator while treating the depressor.
- The net vector reverses. Instead of lift, you get descent.
"So not only does it matter where we are and what muscle," Melissa summarises, "but what depth we're at. That's complication number one — causing a depression when we really want elevation."
This is why the lateral tail is a superficial injection. It is not primarily to reach the corrugator more accurately. It is to stay above the frontalis fibres you would otherwise deposit product into. The superficial placement is a deliberate avoidance manoeuvre disguised as a targeting instruction.
Injectors who learn the depth as a rule without the reason will eventually apply it inconsistently, because a rule without a mechanism has no defence against a protocol that says otherwise. Injectors who learn the reason cannot get it wrong, because they know what is underneath.
The antagonist consequence, stated generally
The corrugator case is one instance of a relationship Melissa builds the whole of her upper-face teaching on. "It's important to understand not just the vessels but the muscles that are there — what their origin is, what their action is, and what their antagonistic muscles do."
The upper face is a small arena in which one elevator opposes four depressors. The frontalis lifts. The procerus, the corrugator supercilii, the depressor supercilii and the superior fibres of orbicularis oculi pull down. Every neurotoxin injection in this region is a deliberate adjustment to the balance of that pair, and the result the patient sees is the net of the two, not the effect on the muscle you aimed at.
That has a specific implication that is worth stating on its own line: in the upper face, every error has a direction. Weaken a depressor you did not intend to and you get more lift than you planned — sometimes a spock brow, sometimes asymmetry. Weaken the elevator you did not intend to and you get descent, which is the complication patients notice, dislike and remember.
The lateral corrugator tail is dangerous specifically because it is the point where the two muscle groups physically overlap, which means it is the point where an error of a few millimetres in depth flips the sign of the result.
Marking the muscle rather than remembering a line
The second half of Melissa's corrugator teaching is about how you decide where the lateral tail actually ends — and here she names the rule she was taught and then explicitly supersedes it.
"We want to stay medial to the mid-pupillary line. That was old school. That's how I learned many years ago. But I want you guys to take it one step further. I want you to really mark out the movement, mark out the muscle, and stay medial to that."
The mid-pupillary line is a population average applied to an individual. It is a reasonable first approximation and a poor final answer, because corrugator length and lateral extent vary considerably between patients — and the whole problem with the lateral tail is that it is defined by where this patient's muscle stops.
Her protocol replaces the remembered line with an observed one:
Have the patient animate. "Botox works on movement, so we want our patients to show us a movement. We would have them make an angry face so that we could see the depression." A corrugator at rest tells you very little. A contracting corrugator shows you its borders.
Mark what actually moves. Not what should move. Melissa marks the borders of the glabellar complex on the animating patient — the procerus with its characteristic horizontal line, the corrugator with its medial head and lateral tail — and works from those marks.
Stay medial to your own mark. "This is going to be the safe zone." The boundary is patient-specific and drawn, not recalled.
Assess static and dynamic separately. "Really look at the patient staying still, and then the movement." Resting brow position, asymmetry and any compensatory frontalis recruitment change the plan before a single point is chosen. Everyone is somewhat asymmetrical, and asymmetry is something to compensate for deliberately rather than discover afterwards. The distinction between what the muscle is doing and what is etched into the skin is developed in dynamic vs static wrinkles.
Standard site maps such as those in Botox injection sites and the Botox face chart are useful for organising the plan. They are not a substitute for marking the muscle in front of you, and the lateral corrugator tail is the single point where that difference most reliably costs you the result.
Angle is the third variable
Depth and position are two of the three variables Melissa names. The third is the one injectors rarely audit.
"You have to be careful of where your needle is pointing and the angle, because you want to make sure you're not affecting the muscles around — because that's when you're going to have a negative effect."
At the lateral tail, angle is a live risk in two directions. Angled downward and laterally you are heading toward the orbital rim and the supraorbital region, which is the route by which glabellar toxin produces a true eyelid ptosis rather than the brow ptosis discussed above. Angled deep you are in the frontalis fibres. A correctly sited, correctly dosed injection delivered on the wrong trajectory deposits product along that trajectory, not at the point where the skin was penetrated.
The medial head has its own angle consideration, though it is vascular rather than muscular: the supratrochlear neurovascular bundle runs deep in this region, beneath the corrugator, near its bony origin. A deep medial injection is an injection into that neighbourhood. For neurotoxin the volumes and consequences differ from filler, but the anatomical company you are keeping is the same, and it is why the glabella is the region it is.
What changes on Monday
Stop treating corrugator depth as one number. It is two, and the reason for the second one is the frontalis, not the corrugator.
Stop taking the lateral boundary from the mid-pupillary line. Mark it on an animating patient and stay medial to your own mark.
And when you plan any upper-face injection, ask the antagonist question before the injection-point question: which muscles are within reach of this deposit, which of them elevate, which depress, and what is the net vector if I am a couple of millimetres off? In the glabellar complex that question has a real answer, and it is the difference between the lift you promised and the heaviness the patient is going to call you about.
These techniques and depths reflect Melissa Pulcini-Buttine's clinical practice as taught in Empire Medical Training's hands-on curriculum. Technique is learned under supervision; this article is educational and is not a substitute for training.
The layered relationship between corrugator, frontalis and orbicularis is difficult to hold from diagrams and straightforward once dissected. Empire teaches it directly in anatomical based aesthetics training and special anatomical cadaver aesthetics training, where the glabellar complex is opened and the interdigitation is visible rather than described. Core neurotoxin competence is covered in cosmetic neurotoxins training.
Melissa Pulcini-Buttine, PA — physician assistant of two decades; professor of anatomy and physiology for ~14 years; faculty member, Empire Medical Training; founder of an aesthetics practice in Greenwich, Connecticut.
Related guides in this cluster
Part of Facial Muscle Anatomy for Neurotoxin.
 Clinical GuideMost Neurotoxin Complications Are Diffusion, Not Misplacement — Rethinking Root CauseMost neurotoxin complications come from diffusion into an adjacent muscle, not from injecting the wrong site. Here is how to tell which
 Clinical GuideThe Crow's Feet Trap — How Chasing Lateral Cheek Lines Reaches the ZygomaticusA zygomaticus botox complication after crow's feet treatment has one usual cause — chasing lateral cheek lines too low and too deep. Th
 Clinical GuideDepressor Anguli Oris, DLI and Mentalis — Three Overlapping Muscles, Millimetres ApartDepressor anguli oris anatomy is a depth problem, not a map problem. The DAO, DLI and mentalis overlap in layers, and confusing them al
Train with Empire
This guide is clinical education. The technique behind it is taught hands-on, on live patients, with faculty beside you.
Explore Botox Training & Certification →Disclaimer
This article reflects the clinical opinions and experience of Melissa Pulcini-Buttine, PA, an independent faculty member contributing to Empire Medical Training's curriculum. The views expressed are the author's own and do not necessarily represent those of Empire Medical Training.
It is professional education, not medical advice, and is no substitute for hands-on training or independent clinical judgment. Licensed clinicians remain responsible for their own patient selection, technique and outcomes, for verifying current product labelling, and for practising within their scope and applicable law. Empire Medical Training accepts no liability for reliance on this content.