








Neurotoxin units vs volume is the single arithmetic relationship that separates an injector who can work confidently across products, vial sizes and indications from one who can only repeat a memorised recipe. Dr. Chris Croley, Chief Medical Officer at Empire Medical Training, opens this topic in Empire's hands-on curriculum with a statement that sounds almost too simple to be worth saying out loud, and then spends the rest of the session proving how much follows from it.
"If I have 100 units in this vial, it doesn't matter how much fluid I put into the vial. It's still 100 units. That never changes."
Everything else in reconstitution is downstream of that sentence. The powder in the vial is a fixed quantity of biological activity. Saline is not an ingredient in the dose; it is a delivery vehicle. Adding more of it does not add toxin, dilute potency in any pharmacological sense, or weaken the product. It changes one thing only: how many millilitres you must push through the needle to deliver a given number of units. This article builds the full conversion logic from that anchor, and it is the hub the rest of Empire's reconstitution and dosing resources hang from.
The three quantities, and which one you control
There are exactly three numbers in play, and confusion almost always comes from collapsing two of them into one.
Units in the vial. Fixed at manufacture. A 100 Unit vial holds 100 Units whether it sits unopened for a month or you reconstitute it with 1 mL or 5 mL. You do not control this except by choosing which vial to open.
Concentration. Units per unit volume, usually expressed as Units per 0.1 mL in aesthetic practice. This is the number you create when you choose a diluent volume. It is the only variable in the chain that is genuinely yours.
Injected volume. The number of millilitres that leaves the syringe at a given point. Multiplied by concentration, this produces the delivered dose.
Written as a relationship:
Concentration = Units in vial ÷ diluent volume Delivered dose = concentration × injected volume
Which rearranges to the form you will actually use at the bench:
Injected volume = desired dose ÷ concentration
Dosing is prescribed in units. Volume is what your hand executes. The conversion between them is the concentration you created when you drew up the saline, and it is your responsibility to know it before you touch the patient.
Working the arithmetic on a 100 Unit vial
Croley teaches the arithmetic on the vial size most injectors handle daily. The convention in aesthetics is to anchor everything to 0.1 mL because most on-label facial dosing is written in 0.1 mL aliquots.
Take a 100 Unit vial and reconstitute with 2.5 mL of saline. That is 100 Units in 2.5 mL, or 40 Units per mL, or 4 Units per 0.1 mL. Reconstitute the same vial with 1 mL instead and you have 100 Units in 1 mL, 100 Units per mL, 10 Units per 0.1 mL.
As Croley puts it: "If I put 2.5 mL into the vial, that means for every 0.1 mL is four units. But let's say I change that and I put one millilitre into the vial. That means if I do a one millilitre reconstitution, for every 0.1 mL it's going to equal ten units."
The consequence is the part injectors underestimate. The same 0.1 mL of fluid, pushed with the same thumb pressure, through the same needle, into the same muscle, is 4 Units in one scenario and 10 Units in the other. Nothing visible has changed. Everything pharmacological has.
Extend the table across the dilutions an aesthetic practice realistically uses:
| Diluent added to a 100 Unit vial | Units per mL | Units per 0.1 mL | Volume needed for 4 Units | Volume needed for 20 Units |
|---|---|---|---|---|
| 1 mL | 100 | 10 | 0.04 mL | 0.2 mL |
| 1.25 mL | 80 | 8 | 0.05 mL | 0.25 mL |
| 2 mL | 50 | 5 | 0.08 mL | 0.4 mL |
| 2.5 mL | 40 | 4 | 0.1 mL | 0.5 mL |
| 4 mL | 25 | 2.5 | 0.16 mL | 0.8 mL |
| 5 mL | 20 | 2 | 0.2 mL | 1 mL |
Read the last two columns across. A 20 Unit glabellar treatment occupies 0.2 mL of tissue at a 1 mL reconstitution and 1 mL of tissue at a 5 mL reconstitution — a fivefold difference in the fluid volume deposited into the same five points, for an identical delivered dose. That fivefold difference is the entire subject of concentration as a clinical instrument, and it is why reconstitution is a treatment-planning decision rather than a back-office task.
Why 0.1 mL became the anchor, and where the anchor breaks
Most aesthetic dosing is written in 0.1 mL aliquots because most on-label aesthetic dosing was studied that way. The BOTOX Cosmetic label instructs 0.1 mL (4 Units) into each of five sites for glabellar lines, a total of 20 Units; 0.1 mL (4 Units) into each of three sites per side for lateral canthal lines, a total of 24 Units; and 0.1 mL (4 Units) into each of five forehead sites alongside the five glabellar sites, a recommended total of 40 Units. XEOMIN and JEUVEAU both specify 4 Units per site into five glabellar sites for a maximum recommended 20 Units. At 4 Units per 0.1 mL, dose and volume line up so cleanly that many injectors stop distinguishing them.
Two situations break the habit, and both appear in ordinary aesthetic practice.
The first is DYSPORT, whose label does not use 0.1 mL as the glabellar aliquot at all. DYSPORT's glabellar dose is 50 Units divided into five equal aliquots of 10 Units. At the label's 20 Units per 0.1 mL concentration, 10 Units is 0.05 mL. At the label's 12 Units per 0.1 mL concentration, 10 Units is 0.08 mL. The DYSPORT label spells this out directly, noting that dose can be decreased or increased by administering a smaller or larger injection volume — 0.05 mL for a 50% decrease, 0.08 mL for a 20% decrease, 0.15 mL for a 50% increase. An injector who has internalised "one tick mark equals one injection point" and transfers that habit to DYSPORT will deliver the wrong dose.
The second is the BOTOX Cosmetic platysma band indication, which uses 0.05 mL (2 Units) into each of four sites in the upper platysma and 0.025 mL (1 Unit) into five sites on each vertical band. At 4 Units per 0.1 mL, a 1 Unit aliquot is a quarter of the smallest confident mark on most syringes. Volumes that small are a syringe-selection problem before they are a technique problem, and Empire covers that separately in the resource on syringe graduation and calibration.
The reverse calculation: from a dose you were taught to a volume you can see
Trainees are usually handed a dosing plan in units — 20 to the glabellar complex, 10 across the frontalis, 2 per side to the depressor anguli oris. Converting that plan into syringe marks is the step that has to become automatic.
Work it as a ratio. If your reconstitution gives 4 Units per 0.1 mL and you want 2 Units, you need half of 0.1 mL, which is 0.05 mL. If your reconstitution gives 10 Units per 0.1 mL and you want 2 Units, you need one fifth of 0.1 mL, which is 0.02 mL. Same dose. Two and a half times the difference in deposited fluid.
Croley's teaching example runs in exactly this direction. Discussing the perioral field, where the depressor anguli oris sits immediately alongside the depressor labii inferioris, he describes deliberately choosing a tighter concentration and then executing a very small volume: "Maybe we would use something like a one millilitre reconstitution. So for me to deliver two units I would only go to this part of the syringe. Tiny, tiny dose. So it doesn't go over here."
Run the same logic in the opposite direction for a wide-field indication and you reach the same destination by the other road. Croley: "When we start talking about areas like hyperhidrosis or sweating... in those situations, we want that neurotoxin to spread out over a wide surface area, so we get the effect of it. So how do we deliver those number of units over a wide surface area? We put more fluid."
These figures reflect Dr. Croley's clinical practice as taught in Empire Medical Training's hands-on curriculum. Technique is learned under supervision; this article is educational and is not a substitute for training.
The vial ledger: units are also how you count what you have left
The units-not-volume discipline has a second payoff that has nothing to do with safety and everything to do with running a practice.
A 100 Unit vial contains 100 units of treatment capacity. At a 20 Unit glabellar dose that is five treatments, whether you reconstituted with 1 mL or 5 mL. Injectors who think in volume routinely misjudge this, because a 5 mL reconstitution looks like far more product than a 1 mL reconstitution and a heavily diluted vial empties fast in millilitre terms while delivering exactly the same number of units.
Two practical consequences follow. First, when you change your standard reconstitution you must re-baseline your expectations about how many patients a vial covers in millilitres, not in units — the unit count has not moved. Second, every millilitre of reconstituted product left in a syringe hub or a needle is a real number of units discarded, and that number rises as concentration rises. At 10 Units per 0.1 mL, a 0.05 mL residue is 5 Units. At 2 Units per 0.1 mL the same residue is 1 Unit. Concentrated reconstitutions make dead space expensive.
Mixing the vial: the mechanical half of the job
Arithmetic assumes the solution is homogeneous. Croley is explicit that this is not automatic, and he draws attention to a detail injectors miss because the powder is nearly invisible.
"In Botox it just looks like a small gray ring at the bottom. It almost looks like there's no product in there at all, and we think we received an empty vial. With some of the others, they're going to have a little powder in the bottom. So we put our fluid into the vial. We gently swirl the vial. We also turn it upside down in case any of it is stuck up in the cap."
Inverting the vial after reconstitution is the step that gets skipped. Lyophilised material and residual product can sit against the stopper, and if it is not brought into solution it is not in your syringe. Every current US label also instructs that the diluent be introduced slowly, that the vial be discarded if the vacuum does not draw saline in, and that the product be swirled rather than shaken. The vacuum check is a genuine integrity test, not a formality.
What the label says about the diluent itself
Every botulinum toxin type A product approved in the United States specifies preservative-free 0.9% Sodium Chloride Injection, USP as the diluent. Many practices, including Empire's teaching practice, use bacteriostatic saline instead, which contains benzyl alcohol as a preservative.
Croley addresses this directly: "What's on label is normal saline preservative free. Many of us will use bacteriostatic saline. That bacteriostatic saline has a preservative in it. It's called benzyl alcohol. And that gives us a little bit of a numbing, or helps the patients tolerate — there's less discomfort with the procedure. The preservative, to the best of our knowledge, doesn't change the performance of the toxin at all."
That is an off-label diluent choice with a real published evidence base behind it, including randomised comparisons of injection pain, and it deserves a piece of its own rather than a paragraph here. Empire's companion resource on bacteriostatic versus preservative-free saline works through what benzyl alcohol does, what the trials showed, and what the choice means for documentation.
Four failure modes the arithmetic prevents
Changing the reconstitution without changing the plan. An injector who normally runs 2.5 mL reconstitutes at 1 mL to tighten a perioral treatment, then completes the rest of the face on autopilot at 0.1 mL per point. Every upper-face point receives 10 Units instead of 4. A 20 Unit glabellar plan becomes 50 Units.
Inheriting a vial. A colleague reconstituted it. You did not. If the concentration is not written on the vial, you do not know the dose you are about to give — you know only the volume. Labelling the vial with units per 0.1 mL and the reconstitution time is a one-second habit that closes this hole.
Communicating in volume. "Give her a tenth in each corrugator" is not a dose. It is a dose only in combination with a concentration that the person hearing it may not share. Croley's rule is unambiguous: "Always remember we're dosing on number of units, not on volume. So I'm not telling you point one or 0.15 or 0.05 — I'm telling you how many units to inject. And then you're having to actually know how much volume it takes to deliver those number of units."
Carrying a habit across products. The 0.1 mL aliquot that is correct for BOTOX Cosmetic, XEOMIN and JEUVEAU at 4 Units per 0.1 mL is not correct for DYSPORT at its label glabellar concentrations, and units of one product are not convertible into units of another in any case. Every US botulinum toxin label carries language to that effect, and Empire treats it as a separate topic because the reasoning behind it is a pharmacology question rather than an arithmetic one.
Building the habit at the chairside
Three checks, run in order, before any neurotoxin leaves a syringe.
- State the concentration out loud. "One hundred units in two and a half millilitres. Four units per tenth." If you cannot say it, do not inject from that vial.
- Convert the plan into volumes before you draw up, not while the needle is at the skin. Write the volumes on the treatment record next to the unit doses.
- Confirm the syringe you are holding matches the volumes you calculated. A 0.02 mL aliquot and a 0.2 mL aliquot are not equally readable on every barrel, and reading error is a dosing error.
This is also the sequence Empire teaches trainees to use when they encounter a product, a vial size or an indication they have not handled before. The arithmetic does not change. Only the inputs do — which is precisely why owning the arithmetic is more durable than memorising any single recipe.
Injectors who want to work through reconstitution and dosing with live product and supervision can do so in Empire's Complete Botox Training and Cosmetic Neurotoxins Training workshops, where the vial work in this article is performed rather than read. Injectors building out regional dosing plans will also find Empire's material on frontalis dosing, injection site mapping and dynamic versus static wrinkles useful alongside it, and those extending into combination work can look at Advanced Botulinum Toxin and Filler Training.
Where this sits in the cluster
This article is the hub for Empire's reconstitution and dosing resources. The companion pieces take one branch each: the on-label reconstitution reference across all five US neurotoxins; why a unit of one product is not a unit of another; what benzyl alcohol actually contributes when you reach for bacteriostatic saline; how concentration governs the field of effect; the perioral corridor, where the tightest concentration earns its keep; the wide-field logic behind dilute reconstitution for hyperhidrosis; and the syringe graduation problem that makes three injectors giving the same dose see three different marks.
Each of those starts from the sentence at the top of this page. The vial holds what it holds. Volume is what you change.
Every guide in this cluster
 Clinical GuideOn-Label Reconstitution Across the US Neurotoxins — A Reference Table for InjectorsA complete on-label neurotoxin reconstitution chart for Botox, Dysport, Xeomin, Jeuveau and Daxxify — vial sizes, diluent volumes and u
 Clinical GuideWhy a Unit of Botox Is Not a Unit of DysportBotox units vs Dysport units are not the same measure. Units are defined by each manufacturer's own potency assay — here is why no conv
 Clinical GuideBacteriostatic vs Preservative-Free Saline — What the Benzyl Alcohol Actually DoesBacteriostatic saline for neurotoxin reconstitution is off-label but well studied. What benzyl alcohol does to injection pain, potency
 Clinical GuideConcentration as a Clinical Instrument — How Dilution Governs DiffusionNeurotoxin dilution and diffusion, worked as a decision. When to choose a tighter concentration, when to choose a looser field, and wha
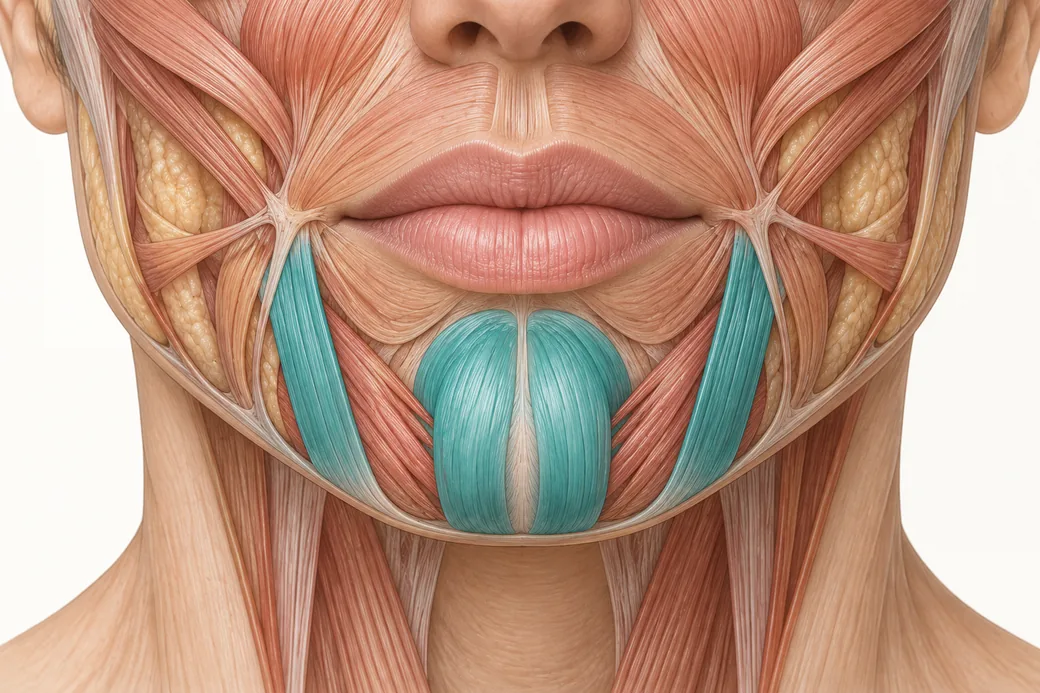 Clinical GuideThe Perioral Field — Why the DAO Corridor Demands Your Tightest ConcentrationThe DAO sits millimetres from the depressor labii inferioris. Why concentration, not just placement, is what keeps a perioral neurotoxi
 Clinical GuideInsulin, 0.5 mL and 1 mL Syringes — Why Three Injectors Drawing "the Same Dose" See Three Different MarksUsing an insulin syringe for neurotoxin dosing means reading insulin units, not toxin units. How graduations, calibration and dead spac
 Clinical GuideDose Equals Duration — The Principle That Predicts How Long a Neurotoxin Complication Will LastDose equals duration is the principle that lets clinicians forecast how long a neurotoxin complication will last — and why you still ca
 Clinical GuideExtrapolating Doses to Off-Label Muscles — A Reasoning FrameworkOff-label neurotoxin dosing has no reference table. Dr. Chris Croley's inference method — size, density, activity and analogy — gives y
Train with Empire
This guide is clinical education. The technique behind it is taught hands-on, on live patients, with faculty beside you.
Explore Botox Training & Certification →Disclaimer
This article reflects the clinical opinions and experience of Dr. Chris Croley, Chief Medical Officer, Empire Medical Training, an independent faculty member contributing to Empire Medical Training's curriculum. The views expressed are the author's own and do not necessarily represent those of Empire Medical Training.
It is professional education, not medical advice, and is no substitute for hands-on training or independent clinical judgment. Licensed clinicians remain responsible for their own patient selection, technique and outcomes, for verifying current product labelling, and for practising within their scope and applicable law. Empire Medical Training accepts no liability for reliance on this content.