








The needle vs cannula filler question is usually settled for an injector by someone who is selling something. The claim arrives in a compressed and appealing form — use a cannula, it can't enter a vessel — and because it is half true, it survives contact with experience for a long time.
Melissa Pulcini-Buttine, PA, teaches it differently, and her framing is worth taking literally rather than as a hedge: "What do you choose, a needle or a cannula? Neither is 100% safe. You could either put your sharp needle right into a vessel, or you can cannula right into it."
She is correct, and unusually the literature is detailed enough to say exactly how correct, where the cannula advantage is real, and where it evaporates. This article sets out what the evidence supports, what it does not, and what should actually drive device selection in the territories where the consequences are worst.
What the cannula advantage genuinely is
Start by conceding the strong part of the case, because injectors who hear only the rebuttal will over-correct.
The largest comparative dataset is a retrospective survey of 370 board-certified dermatologists reporting approximately 1.7 million syringes of filler (Alam M, Kakar R, Dover JS, et al. Rates of Vascular Occlusion Associated With Using Needles vs Cannulas for Filler Injection. JAMA Dermatol. 2021;157(2):174-180. PMID 33377939).
The headline numbers are substantial and should not be minimised:
| Device | Vascular occlusions | Rate |
|---|---|---|
| Needle | 176 in 1,128,192 syringes | 1 per 6,410 |
| Cannula | 13 in 531,466 syringes | 1 per 40,882 |
On multivariate analysis, cannula use was associated with 77.1% lower odds of vascular occlusion (P < .001). That is a real effect, in a large dataset, and any argument that pretends otherwise is dishonest.
But the same analysis contains a second finding that is almost never quoted alongside the first: more than five years of injecting experience was associated with 70.7% lower odds of occlusion, and each additional injection performed per week reduced the odds by a further 1%.
Read those two results together and the conclusion changes character. The device is one of two large protective levers, and the other one is the injector. An experienced clinician with a needle and an inexperienced clinician with a cannula are not obviously in different risk categories. The cannula is not a substitute for knowing where you are — it is roughly as protective as knowing where you are, which is a very different claim from the one made at the exhibition stand.
Two further caveats belong on the record. The study is a retrospective survey subject to recall bias, under-reporting of minor events and data entry error, and its population is board-certified dermatologists, which limits generalisability to the broader injector market. The authors themselves decline to issue a device mandate, concluding that appropriate device choice "may depend on patient factors, anatomic site, and the type of defect being treated."
The mechanical rebuttal: gauge, not tip
Here is where the "cannulas cannot enter arteries" claim breaks, and it breaks on a specific number.
Pavicic and colleagues measured the force required to penetrate facial and superficial temporal arteries across 294 penetration procedures in fresh-frozen cephalic specimens, comparing needles and cannulas at matched gauges (Pavicic T, Webb KL, Frank K, Gotkin RH, Tamura B, Cotofana S. Arterial Wall Penetration Forces in Needles versus Cannulas. Plast Reconstr Surg. 2019;143(3):504e-512e. PMID 30589824).
| Device | Penetration force (N) |
|---|---|
| Needle 20G | 1.12 ± 0.29 |
| Needle 22G | 1.08 ± 0.25 |
| Needle 25G | 0.69 ± 0.24 |
| Needle 27G | 0.70 ± 0.29 |
| Cannula 22G | 1.50 ± 0.31 |
| Cannula 25G | 1.04 ± 0.36 |
| Cannula 27G | 0.78 ± 0.35 |
The critical comparison is the bottom row against the fourth: a 27G cannula required 0.78 N and a 27G needle 0.70 N, a difference that was not statistically significant (P = 0.558). The authors' conclusion is unambiguous: 27-gauge cannulas "are not safer than 27-gauge needles."
Note also what the table shows overall — every cannula tested penetrated the artery. What varied was the force required, not whether it was possible. The blunt tip does not confer immunity; it raises a threshold, and the height of that threshold is set by gauge.
A second cadaveric study reached a compatible conclusion by a different route. Ugradar and Hoenig tested blunt microcannulas against the facial artery at the nasolabial fold across 20 hemifaces and found a strong inverse relationship between gauge number and penetration force (r = −0.970, P < 0.01), with 18G and 22G cannulas unable to penetrate the vessel wall at all in their rig (Ugradar S, Hoenig J. Measurement of the Force Required by Blunt-Tipped Microcannulas to Perforate the Facial Artery. Ophthalmic Plast Reconstr Surg. 2019;35(5):444-446. PMID 30624414). Their conclusion: cannulas "smaller than 22G penetrate the facial artery with a low amount of force."
An honest caveat, because it matters: these two studies disagree about the 22G cannula — Ugradar found it could not penetrate, Pavicic found it could, at 1.50 N. Their absolute force values are also an order of magnitude apart, reflecting different rigs, specimen preparation and approach angles, and should not be combined into a single table. What survives both studies is the rank ordering: smaller-bore cannulas perforate arteries more easily, and the smallest are functionally comparable to needles.
That gives you the single most actionable sentence in this article. If you selected a cannula for vascular safety and you selected 27G, you did not buy what you thought you bought.
Why "I would feel it" is not a defence
Injectors who use cannulas often describe a tactile reassurance — the sense that an artery would announce itself as resistance before the cannula entered it.
Tansatit and colleagues tested that directly, advancing a 25G cannula against the frontal branch of the superficial temporal artery across 100 arterial segments in soft-embalmed cadavers under five simulated scenarios (Tansatit T, Apinuntrum P, Phetudom T. A Dark Side of the Cannula Injections: How Arterial Wall Perforations and Emboli Occur. Aesthetic Plast Surg. 2017;41(1):221-227. PMID 28008463).
Two findings matter clinically.
First, a perpendicular cannula-to-artery angle was the essential condition for perforation. A cannula travelling roughly parallel to a vessel tends to displace it. A cannula crossing it at right angles tends to engage it. This converts an abstract safety question into a concrete planning one: the trajectory of your cannula relative to the known course of the regional vessel is a variable you control at the moment you choose your entry point.
Second, and more uncomfortably, the authors report that "the injector cannot discriminate the sensation at the cannula tip between the resistance of a fibrous septum in the way of the insertion and the resistance of encountering an artery."
Facial soft tissue is full of septa. They feel like the thing you are hoping you would notice. The tactile defence does not exist.
The blindness registries: cannulas are in them
The most direct refutation of the "cannula equals safe" claim is that cannula-attributed vision loss is documented in the published literature, repeatedly, with the gauge named.
The Beleznay group maintains the standing review of filler-induced blindness. Two successive updates report device data:
- In the 2019 update covering 48 new cases, device was documented in 16 cases; a needle was used in 10 and a cannula in 6, with cannula sizes ranging from 27G to 23G (Beleznay K, Carruthers JDA, Humphrey S, Carruthers A, Jones D. Update on Avoiding and Treating Blindness From Fillers. Aesthet Surg J. 2019;39(6):662-674. PMID 30805636).
- In the 2024 update covering 365 new cases, device was documented in 38; a needle in 22 (57.9%) and a cannula in 16 (42.1%), with reported cannula gauges from 23G to 27G (Doyon VC, Liu C, Fitzgerald R, et al. Update on Blindness From Filler. Aesthet Surg J. 2024;44(10):1091-1104. PMID 38630871).
Combined, that is at least 22 published cases of filler-induced vision loss in which a cannula was the documented device. And the figure is certainly an undercount: device was recorded in only a third of the 2019 cases and in 38 of 365 in the 2024 series, so the limiting factor is reporting, not occurrence.
The 2019 paper's own prevention guidance states the position plainly: "Some authors recommend a cannula in the belief it is less likely to pierce blood vessels. However, there are cases of vascular compromise from cannulas of various sizes."
Named case material exists too. A case series of six severe vision-loss events includes injections of the nose and forehead performed with 25G cannulas (Thanasarnaksorn W, Cotofana S, Rudolph C, Kraisak P, Chanasumon N, Suwanchinda A. Severe vision loss caused by cosmetic filler augmentation. J Cosmet Dermatol. 2018;17(5):712-718. PMID 30006992).
One further data point deserves careful handling rather than enthusiasm. In the Alam survey, among the 13 cannula-associated occlusions, one involved eye injury (7.7%), compared with two of 176 needle occlusions (1.1%). A single event cannot support a claim that cannula complications are more severe, and the reader should not take it that way. What it does establish is that an ocular injury occurred in the cannula arm of the largest comparative series available.
What the consensus documents actually say — and at what evidence level
Injectors are frequently told that "the guidelines recommend cannulas in high-risk areas." That is broadly accurate and materially incomplete, because the guidance is more qualified than the summary and rests on a weaker evidential base than the phrase "guidelines" implies.
The Global Aesthetics Consensus does recommend blunt cannulas in vascular-risk regions including the glabella, alar base, nose and temple — and in the same document states that "no single injection technology is completely safe" and that "operator technique is more important with regard to safety" (Signorini M, Liew S, Sundaram H, et al. Plast Reconstr Surg. 2016;137(6):961e-971e. PMID 27219265). The same panel warns against relying on a negative aspiration to exclude intravascular placement.
The consensus guidance on visual loss is the source of the gauge rule injectors half-remember: "The cannula size used to inject should be 25G or greater diameter. There is opinion and views that a 27G cannula has a great potential to penetrate arterial walls," adding that thin needles and cannulas of 27G or smaller "may enter vessels and also need high pressure to initiate flow" (Humzah MD, Ataullah S, Chiang C, Malhotra R, Goldberg R. J Cosmet Dermatol. 2019;18(1):71-76. PMID 29885087). That paper is explicit about its own status, noting "a lack of robust Level I data."
A third expert consensus on preventing filler complications is formally designated Level of Evidence V and frames device selection as dependent on physician experience and patient factors rather than issuing a mandate (Urdiales-Gálvez F, Delgado NE, Figueiredo V, et al. Aesthetic Plast Surg. 2017;41(3):667-677. PMID 28411354).
The accurate summary is therefore: region-specific cannula recommendations are expert opinion — Level V. There is no Level I or II evidence recommending a cannula in any specific facial region. That is not an argument against using one. It is an argument against treating the recommendation as settled science when the documents themselves decline to.
The tolerability evidence, which is real and runs both ways
Device choice is not only a vascular question, and the tolerability data are more robust than the safety data because they come from randomised work.
A double-blind, split-face randomised controlled trial of 25 patients receiving 0.5 mL of hyaluronic acid per nasolabial fold found equivalent efficacy between devices, with the cannula side showing significantly less pain (P = .03), oedema (P < .001), redness (P = .01) and haematoma (P < .001) on the day of injection (Hexsel D, Soirefmann M, Porto MD, et al. Dermatol Surg. 2012;38(2):207-214. PMID 22092962). A subsequent split-face pilot with calcium hydroxylapatite found a similar pattern (Beer KR. J Cosmet Dermatol. 2014;13(4):288-296. PMID 25399621).
The nuance comes from a meta-analysis of prospective infraorbital trials, which found needles associated with significantly more ecchymosis and cannulas with significantly more oedema (Nikolis A, Enright KM, Berros P, Sampalis JS. J Cosmet Dermatol. 2023;22(9):2382-2390. PMID 37424173). The trade is not one-directional, and in a region where post-treatment swelling is the patient's chief complaint, that matters.
Finally, on vessel calibre: a cadaveric study of 49 specimens measured facial and periorbital arterial diameters from 0.7 mm (dorsal nasal artery) to 2.1 mm, with up to 23% variation within a single vessel — and the authors explicitly caution that the relationship between cannula diameter and arterial diameter "requires clinical validation in living tissue" (Yi KH, Wan J, Bautzer C, Ascher B, Gold M. Aesthet Surg J. 2025;45(8):836-841. PMID 40317164). Reasoning that your cannula is wider than the artery is not yet a validated safety argument.
A defensible decision framework
Given all of that, what should actually drive the choice in a high-risk region?
1. Decide gauge before you decide tip. If you are selecting a cannula for vascular safety, the consensus position is 25G or larger diameter, and the mechanical data support treating 27G as offering no meaningful advantage over a needle of the same gauge. A 27G cannula chosen for comfort is a legitimate decision; a 27G cannula chosen for vascular safety is a misunderstanding.
2. Plan your trajectory relative to the vessel, not only your entry point. Perpendicular crossings of a known arterial course are the condition under which cannula perforation occurs. Where the anatomy allows, travel with the vessel rather than across it.
3. Do not spend the safety margin you just bought. The frequent failure mode is an injector who selects a cannula and then injects faster, in larger boluses, at higher pressure, because they believe the device has absorbed the risk. The habits that reduce vascular events — low pressure, small aliquots, stopping early — apply identically to both devices.
4. Count your own experience as a variable. The Alam data make experience nearly as protective as device choice. If you are early in your injecting career in a high-risk territory, the honest risk-reduction measure is supervision, not a different instrument.
5. Have the rescue ready regardless. Hyaluronidase available, dose decided, referral pathway known, before the first injection of the day. What dissolution can and cannot achieve is covered in filler dissolve.
Where Melissa puts the device question
Notably, she puts it second.
"Part of the things to decrease any complications would be: am I picking a needle or cannula? And do I know the anatomy, and am I directly getting into it?"
The order in that sentence is the argument. Device selection is a modifier applied to an anatomical decision that has already been made. It adjusts the probability that a given trajectory results in an intravascular event. It does not change where the vessel is, it does not tell you where you are, and — as the registries show — it does not remove the worst outcome from the table.
"Respect anatomy," as she puts it. "Knowledge is power."
The teaching framing in this article reflects Melissa Pulcini-Buttine's clinical practice as taught in Empire Medical Training's hands-on curriculum. Technique is learned under supervision; this article is educational and is not a substitute for training.
Injectors building device judgement on dissected anatomy will find it in Empire's anatomical based aesthetics training and special anatomical cadaver aesthetics training. Foundational filler technique across both devices is covered in complete dermal filler training, and the highest-risk periorbital and nasal territories in master eye and nose injection training. Region-specific reaction patterns in the lips are covered in common lip filler reactions and how to avoid them.
Melissa Pulcini-Buttine, PA — physician assistant of two decades; professor of anatomy and physiology for ~14 years; faculty member, Empire Medical Training; founder of an aesthetics practice in Greenwich, Connecticut.
Related guides in this cluster
Part of Facial Vascular Anatomy for Injectors.
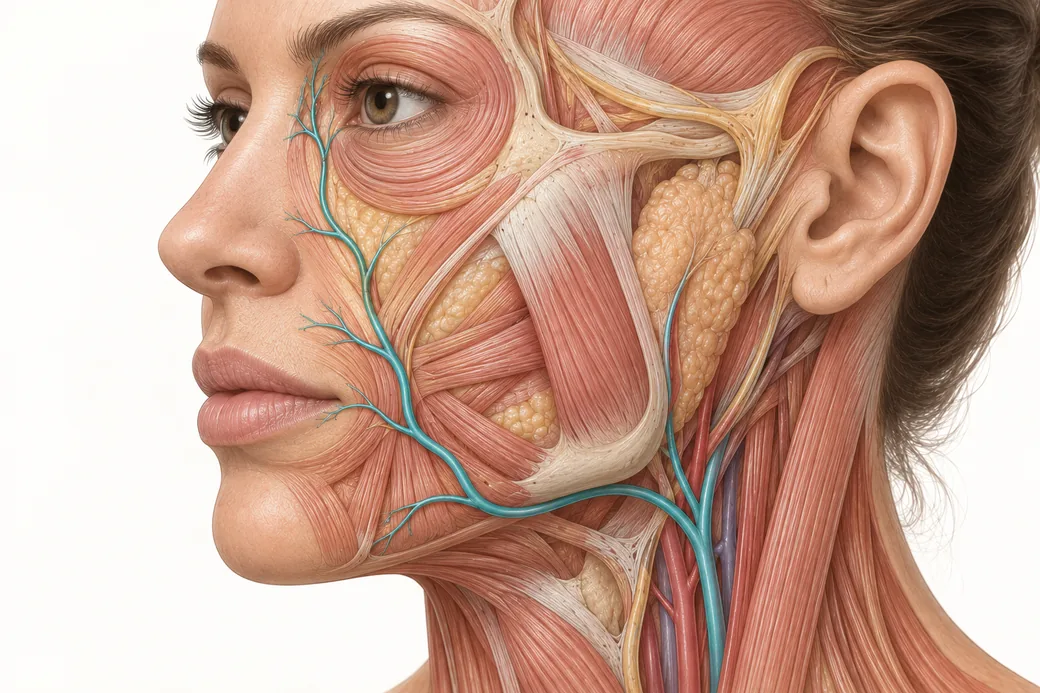 Clinical GuideAnastomoses: Why the Complication Doesn't Appear Where You InjectedFacial artery anastomoses explain why a lip treatment causes nasal skin changes. How arterial connections reframe injector triage and p
 Clinical GuideFiller Vascular Occlusion and Vision Loss: The Glabellar Crossroad, Step by StepHow filler vascular occlusion at the glabella causes vision loss — the retrograde embolic chain from the angular artery to the retina,
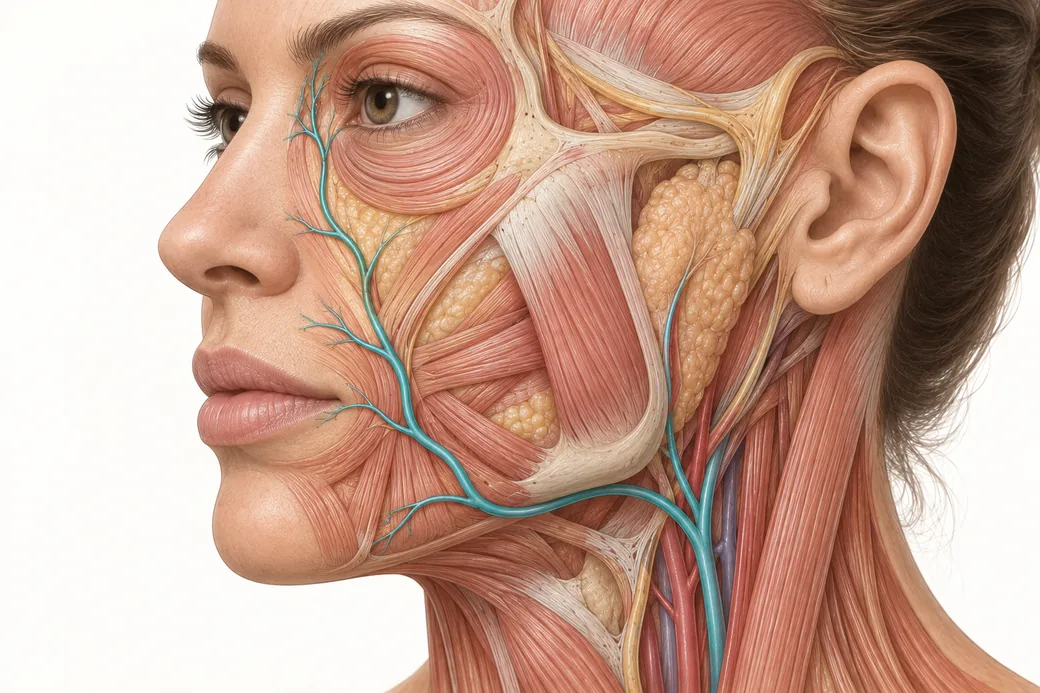 Clinical GuideFacial Artery Variability: Why Landmarks Are Probabilities, Not CertaintiesFacial artery variability in cadaver data — termination points, branch prevalence, tortuosity and depth, and what probabilistic anatomy
Train with Empire
This guide is clinical education. The technique behind it is taught hands-on, on live patients, with faculty beside you.
Explore Anatomical-Based Aesthetics Training →Disclaimer
This article reflects the clinical opinions and experience of Melissa Pulcini-Buttine, PA, an independent faculty member contributing to Empire Medical Training's curriculum. The views expressed are the author's own and do not necessarily represent those of Empire Medical Training.
It is professional education, not medical advice, and is no substitute for hands-on training or independent clinical judgment. Licensed clinicians remain responsible for their own patient selection, technique and outcomes, for verifying current product labelling, and for practising within their scope and applicable law. Empire Medical Training accepts no liability for reliance on this content.