







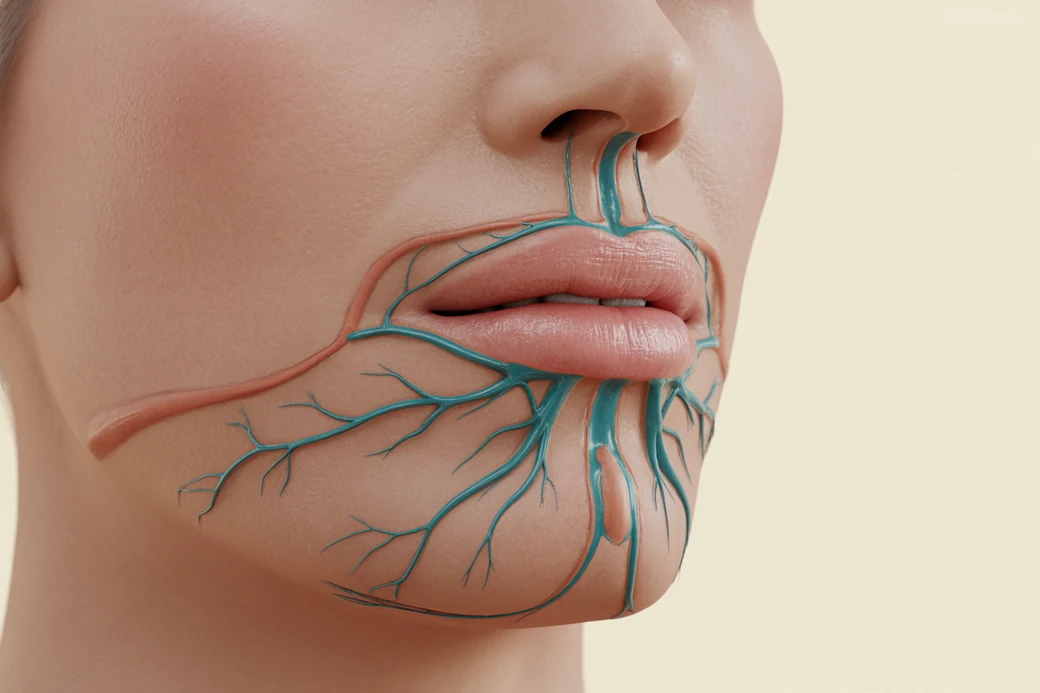
A patient came to me having had a vascular occlusion in her lip at three different practices. Three separate injectors, three separate occasions, the same complication.
The reflex reading is that three injectors were careless. The actual explanation was anatomical, it was discoverable, and the patient had been withholding the history that would have revealed it.
What was actually happening
I took her on because I was intrigued. Three practices hitting the same structure in the same patient is not a run of bad luck; it is a pattern, and patterns have causes.
What we established was that one of her arteries ran more superficially than it does in roughly ninety percent of people. Three different injectors, working to the depth that is correct for the overwhelming majority of patients, had each encountered the superior labial artery where it should not have been.
None of them had done anything textbook-wrong. The textbook simply did not describe her.
Why she had not told anyone
The detail that makes this clinically actionable is why the information had never surfaced.
She had not volunteered it because she was worried I would not take her on as a patient.
That is a rational fear and it produces a dangerous silence. A patient who has had complications elsewhere has learned that disclosing them can mean being turned away, so the patients carrying the highest-value history are the ones most motivated to conceal it.
Once I had the history, everything changed. We went very slowly. I was careful. I aspirated. We went over the emergency protocol before starting, and I had everything ready. I kept her in the office for a long time afterwards and educated her thoroughly. Without that history I might have been considerably less conservative.
How to ask so that you actually get an answer
“Any problems with previous treatments?” invites a no. It sounds like a screening question with a right answer, and the patient knows which answer keeps them in the chair.
Better questions are specific, and framed so that a yes is useful rather than disqualifying:
- “Tell me about every aesthetic procedure you have had, and who did it.”
- “Have you ever had a reaction, a complication, or a result that needed correcting?”
- “Has anything ever been dissolved?”
- “Has anyone ever told you something about your anatomy — that a vessel was in an unusual place, or that they had difficulty?”
Then say the thing that unlocks it: a history of complications does not mean I will decline to treat you. It means I will treat you differently, and more safely. Patients withhold because they expect rejection. Remove the expectation and the information arrives.
Michelle Langston applies the same approach to neurotoxin, asking directly whether a patient has ever had a complication — and a patient reporting twice having had a droopy eyelid after treatment is telling you something anatomical that should change your plan before you draw anything up.
What variation means in practice
Variation is not an exception to anatomy. It is a property of it.
I teach anatomy, and the more heads and cadavers I dissect, the more variation I see — the facial artery in particular differs considerably from patient to patient. Landmarks describe where a structure usually is, which is a probability rather than a guarantee. Depth in particular is variable, and depth is what separates a safe plane from a vessel.
Three consequences follow:
- Your technique should assume you might be wrong about the depth. Small increments, low pressure, slow delivery and aspiration are all hedges against a vessel not being where you expect.
- A previous complication is evidence about this specific patient that no atlas can give you.
- Cadaver work changes what you expect. Reading about variation and seeing it repeatedly in dissection produce different levels of caution.
Treating the patient you now know is a variant
Once you have the history, the plan changes in specific ways:
- Reduce volume per pass and increase the number of passes.
- Reconsider the instrument for that region, understanding that a cannula reduces risk without removing it.
- Consider treating less at one sitting and reviewing, rather than completing the full plan.
- Have the emergency kit out and ready, not merely present.
- Brief the patient before you start on what you are watching for and what you will do.
- Extend the observation period and the follow-up.
- Document the variant prominently in the record, so that future treatments — including by colleagues — begin from the right assumption.
The point for the profession
Three injectors were each individually unlucky and collectively uninformed, because the information that would have protected all of them never travelled.
That is fixable at the level of how we ask, how we record and how we hand over. A patient who has been told that a complication history makes her safer to treat rather than harder to place will tell the next clinician too.
Related guides in this cluster
Part of Vascular Occlusion: Recognition and Response.
 Clinical GuideThe Expected Filler Injection Response — Building the Baseline That Lets You Recognize IschemiaThe expected filler injection response — erythema, edema, ecchymosis — and how a trained normal baseline makes early ischemia recogniza
 Clinical GuideThe Golden Triangle — Why the Filler Deposit Site Isn't Where You Put the Needle InThe filler deposit site sits at the needle tip, not the entry point — about half an inch away, further with a cannula. Why that gap dec
 Clinical GuideImmediate, Early and Late — The Three Windows of Vascular Occlusion OnsetVascular occlusion onset is not one moment. Organize the picture into immediate, early and late windows — detection runs days past the
Train with Empire
This guide is clinical education. The technique behind it is taught hands-on, on live patients, with faculty beside you.
Explore Complete Dermal Filler Training →Disclaimer
This article reflects the clinical opinions and experience of Melissa Pulcini-Buttine, PA, an independent faculty member contributing to Empire Medical Training's curriculum. The views expressed are the author's own and do not necessarily represent those of Empire Medical Training.
It is professional education, not medical advice, and is no substitute for hands-on training or independent clinical judgment. Licensed clinicians remain responsible for their own patient selection, technique and outcomes, for verifying current product labelling, and for practising within their scope and applicable law. Empire Medical Training accepts no liability for reliance on this content.
 Claim Your Prize!