







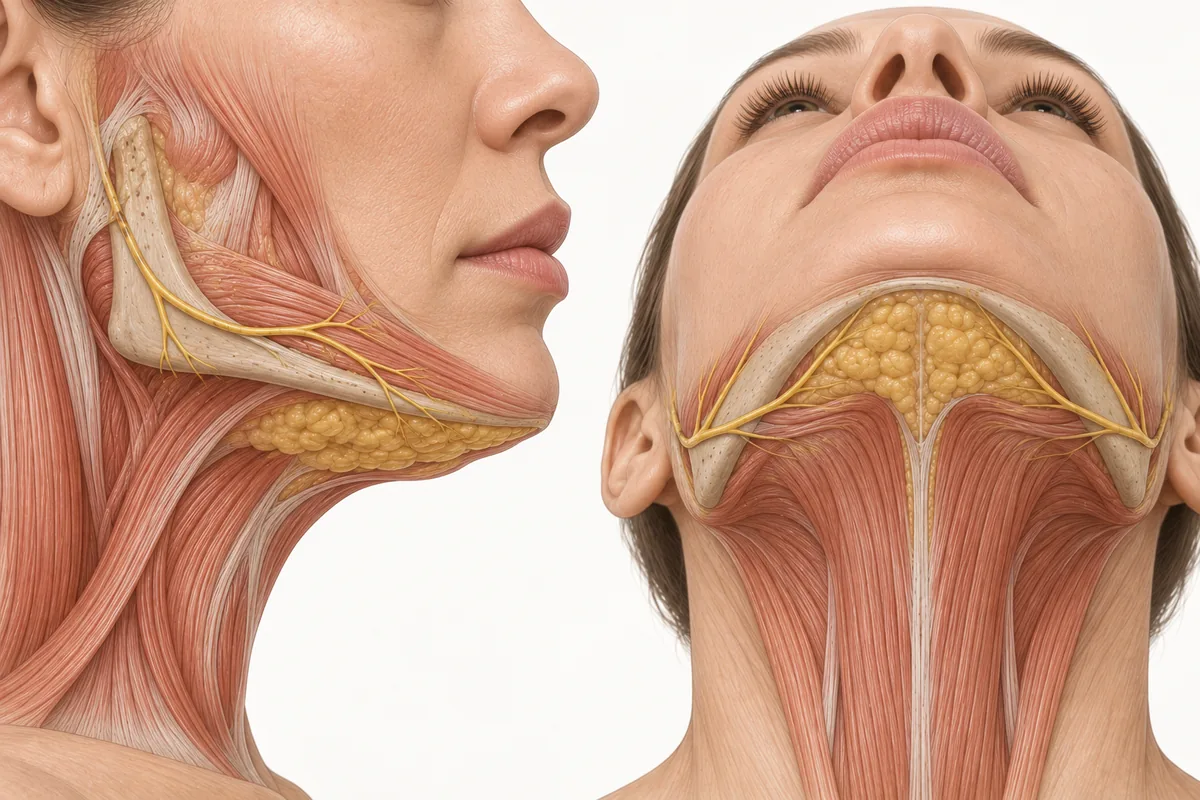
Submental contouring consent is not a signature problem. It is a rehearsal problem. The complaints that follow deoxycholic acid treatment are overwhelmingly generated not by bad injections but by patients who were not walked through what the next ten days would look like — and who then looked in the mirror on day two and saw a stranger with a swollen throat.
I tell patients, before we start, that they are going to look like a bullfrog. I say the word. It gets a laugh in the consultation, and two days later it is the reason they text me a photograph captioned "bullfrog!" instead of "what have you done to me."
That is the whole thesis of this article. Naming the worst-looking part of the process in advance converts it from evidence of a complication into evidence that you knew what you were talking about.
Maritza Mejia, FNP — family nurse practitioner; faculty member, Empire Medical Training; founder of Long Island Beauty Bar, New York.
Why this procedure is different
Most injectables look better immediately, or at worst look neutral. This one looks worse first, visibly, in the most public part of the body, for days to weeks — and the visible worsening is the mechanism working.
Deoxycholic acid is a cytolytic drug: it physically destroys adipocyte membranes, and the lysed fat is then cleared by an inflammatory response consisting of macrophage infiltration and fibroblast recruitment. Oedema is the visible signature of that clearance.
The pivotal trial numbers tell the patient's story better than any reassurance:
| Injection-site reaction | Treated (n=513) | Placebo (n=506) |
|---|---|---|
| Oedema / swelling | 87% | 43% |
| Hematoma / bruising | 72% | 70% |
| Pain | 70% | 32% |
| Numbness | 66% | 6% |
| Erythema | 27% | 18% |
| Induration | 23% | 3% |
And the durations that patients actually care about: reactions lasting more than 30 days and occurring in more than 10% of subjects were numbness (42%), oedema/swelling (20%), pain (16%) and induration (13%).
Read the numbness figure again. Two in three patients experience numbness, and it persists beyond 30 days in over 40% of them. Nobody complains about numbness they were warned about. Everybody complains about numbness they were not.
The four things to say before anything is signed
1. "This is not a weight loss treatment"
Say it in those words, early, and say why.
The drug acts locally on a defined fat compartment. Its systemic pharmacokinetics are trivial: after a maximum single dose, plasma deoxycholic acid peaks at a median of 18 minutes at roughly 3.2-fold above the patient's own baseline level, then returns to the endogenous range within 24 hours. It is a bile acid the patient already circulates. There is no systemic fat-dissolving effect and no mechanism by which this changes body weight.
Patients who believe otherwise are not being unreasonable — "fat-dissolving injection" invites the misunderstanding. Correct it in the consultation and you will never have to correct it at the twelve-week review, which is a far worse place to do it.
The corollary is also worth saying: substantial weight gain after treatment can enlarge the adipocytes that remain. The result is durable, not immune to the rest of the patient's life.
2. "You are going to swell, and the swelling is the treatment"
This is the bullfrog conversation. Be specific, and be specific in the right direction — describe the appearance, not just the adjective.
What I tell them: - There will be burning and tenderness during and immediately after the injections. In a controlled study of patient-experience protocols (Dover et al., Dermatologic Surgery, 2016; PMID 27787269), peak pain occurred within one to five minutes of treatment and rated as mild on a visual analogue scale, reduced substantially by 15 minutes, and by four hours was characterised as mild tenderness or achiness. - The area will swell, often markedly, and often more on day two than on day one. - It will feel firm and lumpy. That is induration and it is expected. - Parts of the chin and neck will feel numb, possibly for weeks. - Bruising is common — though the trial data suggest most bruising is a needle effect rather than a drug effect, since placebo subjects bruised at nearly the same rate. - It settles. As oedema settles, the contour becomes easier to see and judge.
Then the reframe, in one sentence: swelling is the treatment, not the complication. A patient who understands that the puffiness is the body clearing dissolved fat will tolerate it. A patient who thinks it is an allergic reaction will call the office at 9pm.
3. "This takes months, and probably more than one session"
The trials allowed up to six treatments at intervals of no less than one month, and the efficacy endpoint was assessed twelve weeks after the final treatment. At that point, 66.5%–70.0% of treated subjects had achieved a one-grade improvement on the clinician-reported scale, versus 18.6%–22.2% on placebo. Two-grade improvement was achieved by only 13.4%–18.6%.
Translate that honestly: this drug reliably moves people one grade and rarely moves them two. A patient expecting a jawline transformation from one vial has been set up to fail by someone — do not let it be you.
The upside is worth stating in the same breath, because it is genuinely good news and it is earned: because adipocytolysis destroys cells rather than emptying them, the reduction lasts. Long-term follow-up of pivotal-trial responders found that 86.4% maintained their one-grade improvement at one year, 90.6% at two years and 82.4% at three years, with no new safety signals.
4. "Here is what is not treatable, and here is what we would do about it"
If the assessment found laxity, bands, gland ptosis or a low hyoid, the patient hears about them before treatment, not in the explanation of why the result is modest.
Ready to put this into practice?
Explore Empire's hands-on, CME-accredited Aesthetic & Injectable Training courses — live patients, expert faculty, and ongoing mentorship.
This is the conversation that most protects you. Saying "your jawline will improve but this band here is a muscle and will need a different treatment" costs thirty seconds and eliminates an entire category of post-treatment dissatisfaction. Patients whose alternatives were explained — thread lifting for a double chin, tightening modalities, chemodenervation for bands, or surgery — do not feel sold to. They feel advised.
Downtime: the number patients actually want
Everybody asks "how long until I look normal." Give them data rather than optimism.
In a 12-month open-label study (Beer et al., Journal of Drugs in Dermatology, 2019; PMID 31524342), during the seven days after the first treatment, 13.3% of subjects missed work and 33.9% missed social or leisure activities. After subsequent treatments, only 2.4%–6.0% missed work and 10.0%–15.7% missed social activities.
Two useful things come out of that. First, a third of patients alter their social plans after the first session — so "there's no downtime" is not a claim the evidence supports and not one to make. Second, the first session is the hard one. Later sessions are substantially easier, and there is a mechanistic reason: less remaining target tissue permitting lower volumes, persistent numbness, and greater tissue integrity from thickened fibrous septae.
Tell patients to schedule the first session with a clear diary behind it. A patient with an event in three weeks is not a candidate this month.
What belongs in the written consent
The conversation and the document are different artefacts and both are required. Empire's guidance on what to include in injectable consent forms covers the general architecture; the submental-specific items are:
- Injection-site reactions by name and by frequency — oedema, hematoma, pain, numbness, erythema, induration, with the trial incidences.
- Duration language — that numbness, swelling, pain and induration can persist beyond 30 days in a meaningful minority.
- Marginal mandibular nerve injury. Occurred in 4% of treated subjects, presents as an asymmetric smile or facial muscle weakness, and all trial cases resolved spontaneously over a median of 44 days, range 1–298 days.
- Dysphagia. Occurred in 2%, in the setting of administration-site reactions, resolving over a median of 3 days, range 1–81.
- Injection-site ulceration and necrosis, associated with injections that are too superficial.
- Injection-site alopecia, for which the label advises considering withholding subsequent treatments until resolution.
- That multiple sessions are usual and that the number is determined by reassessment, not promised in advance.
- That this is not a weight loss treatment and does not tighten skin.
- That the patient consents to standardised photography at baseline and before each subsequent session — including a smiling view.
- A record of the alternatives discussed, including doing nothing.
And what must not be in it: any guarantee of a result. No satisfaction guarantee, no promised grade of improvement, no "you will love it."
The phrase I end every consultation with
Promise the process, not a miracle.
What I am actually committing to is the process: a careful assessment, an anatomically planned map, labelled dosing, honest photographs, and a reassessment before anything further is done. That is a promise I can keep every time. A specific outcome is not.
Patients accept this far better than clinicians expect. What they want is not certainty — they have been on the internet, they know certainty is not on offer. What they want is to feel that the person holding the syringe has a method. Describe the method and the swelling becomes a chapter in a story they are already following.
These figures reflect Maritza Mejia's clinical practice as taught in Empire Medical Training's hands-on curriculum, together with the current FDA prescribing information and the published literature cited above. Technique is learned under supervision; this article is educational and is not a substitute for training.
Injectors who want to work through consultation, assessment and injection on live patients under faculty supervision can find that in Empire's Kybella and Mesotherapy Training, and the wider regional approach in the Neck & Hands Rejuvenation Master Course.
Frequently Asked Questions
How much swelling should patients be warned about?
In the pivotal trials, 87% of treated subjects experienced injection-site oedema or swelling versus 43% on placebo, and swelling persisted beyond 30 days in 20% of subjects. Patients should be told to expect visible, sometimes marked swelling of the submental area, often worse on the second day, and that it represents the inflammatory clearance of lysed fat rather than a complication.
Is deoxycholic acid a weight loss treatment?
No, and it should be stated explicitly in consultation. The drug acts locally on a defined subcutaneous fat compartment. After a maximum single dose, plasma levels peak at roughly 3.2-fold above the patient's own endogenous baseline and return to the endogenous range within 24 hours. There is no systemic lipolytic effect and no mechanism by which it reduces body weight.
How much downtime should patients plan for?
In a 12-month open-label study, 13.3% of subjects missed work and 33.9% missed social or leisure activities in the week after their first treatment. After subsequent treatments those figures fell to 2.4%–6.0% and 10.0%–15.7%. The first session is the disruptive one, and patients should schedule it with a clear diary rather than being told there is no downtime.
What must be in a submental fat reduction consent form?
Named injection-site reactions with their trial frequencies, the fact that several can persist beyond 30 days, marginal mandibular nerve injury and dysphagia with their incidence and resolution data, ulceration and necrosis, alopecia, that multiple sessions are usual, that it is neither a weight loss nor a skin-tightening treatment, consent to standardised photography, and the alternatives discussed. Never a guarantee of result.
How many sessions should patients expect?
Trial subjects received up to six treatments at intervals of no less than one month. Twelve weeks after the final treatment, 66.5%–70.0% had a one-grade improvement and only 13.4%–18.6% a two-grade improvement. The honest framing is that the drug reliably moves patients one grade, rarely two, and that the number of sessions is decided by reassessment rather than promised at the outset.
Disclaimer
This article reflects the clinical opinions and experience of Maritza Mejia, FNP, an independent faculty member contributing to Empire Medical Training's curriculum. The views expressed are the author's own and do not necessarily represent those of Empire Medical Training.
It is professional education, not medical advice, and is no substitute for hands-on training or independent clinical judgment. Licensed clinicians remain responsible for their own patient selection, technique and outcomes, for verifying current product labelling, and for practising within their scope and applicable law. Empire Medical Training accepts no liability for reliance on this content.



