







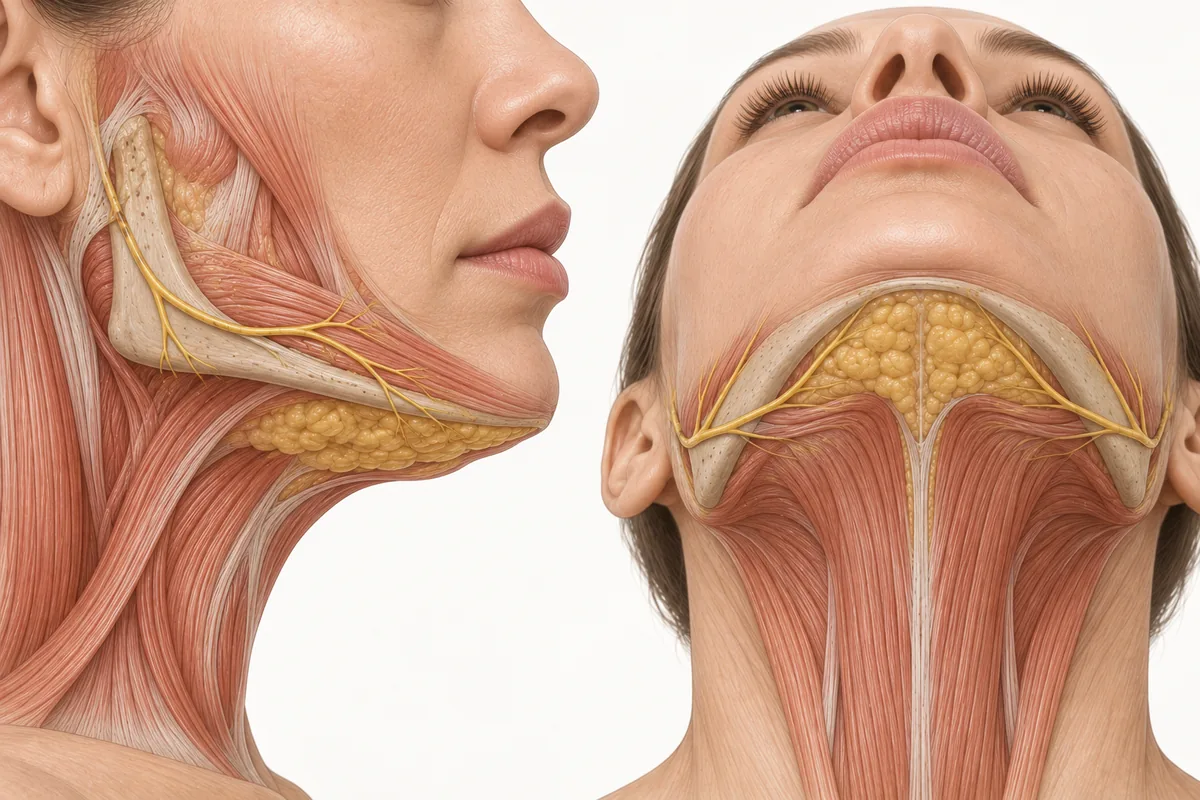
The Kybella retreatment interval on the label is a floor, not a schedule. Up to six single treatments may be administered at intervals of no less than one month — and a great many patients are retreated at exactly one month by clinicians who have mistaken the minimum for the recommendation. The problem is that the drug's own inflammatory response routinely outlasts that interval, which means a meaningful proportion of second sessions are planned against a neck the injector cannot actually see yet.
Reassess before retreating. Not because the label says so in those words, but because you cannot dose a compartment whose size you are misreading.
Maritza Mejia, FNP — family nurse practitioner; faculty member, Empire Medical Training; founder of Long Island Beauty Bar, New York.
What the labelling actually requires
Three instructions, and they are more demanding together than either is alone:
- Up to 6 single treatments may be administered at intervals no less than 1 month apart.
- Prior to each treatment session, palpate the submental area to ensure sufficient submental fat.
- A single treatment may use up to 50 injections of 0.2 mL — a maximum of 10 mL — at an area-adjusted dose of 2 mg/cm².
The first sets a minimum. The second sets a condition. Nothing in the labelling says a patient should be retreated at one month; it says they may not be retreated sooner, and that you must confirm there is fat there before you do.
The efficacy data attach to a different timepoint entirely. In the pivotal trials, the primary endpoint was assessed 12 weeks after the final treatment. That is the interval at which the drug's effect was measured, and it is a reasonable anchor for when a result — as opposed to a tissue state — can be judged.
The swelling curve, and why one month is often too early
From the histology, the inflammatory arc is stereotyped: adipocytolysis and neutrophilic inflammation at Day 1; reduced inflammation with haemorrhage and lipid lakes by Day 3; prominent adipocytolysis with lipid-laden macrophages in the septae at Day 7; and by Day 28 inflammation largely resolved, leaving septal thickening, neovascularisation and atrophy of fat lobules (Walker et al., Dermatologic Surgery, 2020; PMID 30883481).
"Largely resolved at Day 28" is the source of the one-month convention, and at the tissue level it is reasonable. At the patient level it is optimistic. The pivotal trial safety data report that adverse reactions lasting more than 30 days and occurring in more than 10% of subjects were injection-site numbness (42%), oedema/swelling (20%), pain (16%) and induration (13%).
One patient in five still has swelling past the thirty-day mark. One in eight still has palpable induration. If you retreat at day 30 on principle, roughly a fifth of the time you are mapping a neck that is still inflated and palpating a compartment that is still firm.
What I teach, and what matches how the swelling behaves clinically: expect the visible inflammation to be settling by around four to six weeks, with contour becoming genuinely readable after that. If a patient is still visibly swollen, wait a couple more weeks and reassess. By twelve weeks you are looking at the result.
The three-signal test before you open the next vial
Before a retreatment I want three things to agree. If they disagree, the answer is to wait.
Signal 1 — Photographs
Standardised views, taken at the same distance, camera height, head position, lighting and background as the baseline set. Frontal, 45° oblique and profile, neutral expression, plus a smiling view.
You are comparing a photograph to a photograph, not a photograph to a memory. Memory is a systematically biased instrument here: both you and the patient want improvement, and both of you last saw this neck when it was swollen.
The profile view is the one that answers the question. The cervicomental angle is where a submental fat reduction shows up, and it is the view where residual oedema is hardest to mistake for contour.
Signal 2 — Palpation
This is the label's own requirement, and it is the most informative of the three.
Soft, compressible, pinchable tissue across the intended footprint means fat remains and the compartment can take another session.
Firm, boggy, non-pinchable tissue means you are feeling induration, not fat. Induration is thickened, inflamed, remodelling tissue. It is not a target, it will not respond to a cytolytic drug the way fat does, and its presence means the field has not finished.
A thin pinch where there used to be a thick one is a success signal, and it is also a stop signal. The compartment has done what you asked. Injecting a planned volume into a compartment that no longer holds it pushes the drug towards the dermis, and the label associates too-superficial injection with skin ulceration and necrosis.
Treat what you can pinch. That rule does not expire after session one.
Ready to put this into practice?
Explore Empire's hands-on, CME-accredited Aesthetic & Injectable Training courses — live patients, expert faculty, and ongoing mentorship.
Signal 3 — The patient's own report
Two questions: "Does it still feel tight or firm to you?" and "Is it still changing?"
A patient who says the area is still settling week to week is describing an unfinished process. A patient who says it has looked the same for three or four weeks has given you a plateau, and a plateau is what you retreat against.
What residual oedema looks like versus a real result
| Feature | Residual oedema | Settled result |
|---|---|---|
| Symmetry | Often subtly asymmetric | Symmetric |
| Texture on palpation | Firm, boggy, indurated | Soft, or thin and compressible |
| Skin | May be tight, occasionally erythematous | Normal |
| Trajectory | Still changing week to week | Stable for 3–4 weeks |
| Profile view | Convexity retained but "inflated," ill-defined | Convexity reduced, cervicomental angle crisper |
| Patient report | "It still feels swollen/tight" | "It's stopped changing" |
One more discriminator worth knowing: oedema is soft-tissue volume distributed over the treated field and it tends to blur the jawline margin. A residual fat deposit is focal and pinchable. If you can pinch it, it is probably fat. If you can only press it, wait.
Deciding how many more sessions
The trials allowed up to six, and the real-world number is usually lower. The honest answer to "how many will I need" is that it is determined by reassessment, not predicted at the outset — and the reason is that the compartment shrinks under treatment, so each session's dose is derived from a smaller area than the last.
The endpoint is not a number of vials. It is one of three conditions:
- The patient is satisfied. This is a legitimate stopping point regardless of grade.
- There is no longer sufficient pinchable fat to treat safely.
- The residual convexity is no longer fat. Once the treatable compartment is gone, what remains is laxity, band, gland, hyoid or skeletal — and none of those improve with another vial. This is the moment to have the modality conversation rather than the dose conversation, whether that is tightening, thread lifting, chemodenervation for bands, or surgical referral.
Set expectations against the trial data: 66.5%–70.0% of treated subjects achieved a one-grade improvement twelve weeks after their final treatment; only 13.4%–18.6% achieved two grades. Most of the value is in the first grade. Chasing a second one with vial after vial in a patient who has already plateaued is how a good result becomes an over-treated neck.
The reassuring part
Patients tolerate waiting far better when they know two things.
Later sessions are easier. In a 12-month open-label study, 13.3% of subjects missed work in the week after the first treatment versus 2.4%–6.0% after subsequent ones. Less remaining target tissue permits lower volumes, prior numbness persists, and thickened fibrous septae mean a more robust tissue bed.
The result you have already achieved is durable. Long-term follow-up of pivotal-trial responders found one-grade response maintained by 86.4% at Year 1, 90.6% at Year 2 and 82.4% at Year 3, with no new safety signals. There is no window closing. Waiting four extra weeks to assess properly costs the patient nothing and costs you the risk of dosing a neck you could not read.
These figures reflect Maritza Mejia's clinical practice as taught in Empire Medical Training's hands-on curriculum, together with the current FDA prescribing information and the published literature cited above. Technique is learned under supervision; this article is educational and is not a substitute for training.
Injectors who want to practise reassessment, mapping and retreatment decisions on live patients under faculty supervision can find that in Empire's Kybella and Mesotherapy Training. For the patients whose residual convexity turns out not to be fat, the Neck & Hands Rejuvenation Master Course covers the modalities that plan hands over to.
Frequently Asked Questions
What is the minimum interval between deoxycholic acid treatments?
The FDA label permits up to six single treatments at intervals of no less than one month apart. That is a minimum, not a recommendation. The label separately requires palpating the submental area before each session to confirm sufficient submental fat, which means the interval is set by tissue state as much as by the calendar.
How long does swelling last after submental treatment?
Most visible inflammation settles over roughly four to six weeks, but pivotal trial data show reactions persisting beyond 30 days in a substantial minority: numbness in 42% of subjects, oedema or swelling in 20%, pain in 16% and induration in 13%. Roughly one patient in five is still swollen at the one-month mark, which is why retreating strictly at 30 days risks mapping an inflated neck.
When can a submental result actually be judged?
The pivotal trials assessed their primary endpoint 12 weeks after the final treatment, which is a reasonable anchor. Practically, a result is readable once the neck has been stable for three to four weeks, palpates soft rather than indurated, and looks symmetric on standardised photographs — not simply once thirty days have elapsed.
How do you tell residual swelling from residual fat?
By pinch, trajectory and symmetry. Fat is focal, soft and lifts into a pinch; oedema is diffuse, firm or boggy, presses rather than folds, often slightly asymmetric, and is still changing week to week. If you can only press it, wait; if you can pinch it, it is likely fat.
How many treatments do most patients need?
Up to six are permitted, but the number is decided by reassessment rather than predicted in advance, because the treatable compartment shrinks with each session. Stopping points are patient satisfaction, insufficient remaining pinchable fat, or the recognition that the remaining convexity is laxity, band, gland or skeletal rather than fat — none of which respond to another vial.
Disclaimer
This article reflects the clinical opinions and experience of Maritza Mejia, FNP, an independent faculty member contributing to Empire Medical Training's curriculum. The views expressed are the author's own and do not necessarily represent those of Empire Medical Training.
It is professional education, not medical advice, and is no substitute for hands-on training or independent clinical judgment. Licensed clinicians remain responsible for their own patient selection, technique and outcomes, for verifying current product labelling, and for practising within their scope and applicable law. Empire Medical Training accepts no liability for reliance on this content.



